
This Work was originally published in Hungary by Neuropsychopharmacologia Hungarica in 2024 September as supplement. Title: Az aripiprazole kezelések valós környezetben szerzett tapasztalatai skizofréniában és bipoláris affektiv zavar I. tipusában szenvedő betegek körében – ARIAD vizsgálat.
Ágota Mészárossup, Judit Pákó, György Szekeres
Key words
aripiprazole, schizophrenia, bipolar disorder, realworld evidence, adherence, efficiency
Abstract
The partial D2 receptor agonist aripiprazole, initially referred to as a third-generation antipsychotic, has been widely used in the treatment of schizophrenia and bipolar disorder in many countries since the 2000s.
Objective: In the present non-interventional study conducted among psychiatrists, we aimed to collect real-world data (RWD) on experiences gained with aripiprazole related to domestic treatment. During the three-month follow-up period, our primary objectives were to assess treatment retention and patient adherence. Additionally, we analysed the composition of the patient population included in the study, the most common therapeutic decisions for each disorder, the real-world efficacy and safety of the medicine, and the practice of aripiprazole blood level monitoring to support personalized treatment.
Patients and methods: The open-label, multicentre, prospective study included a total of 414 patients aged 18 years and over enrolled by 34 psychiatrists. These patients, diagnosed with schizophrenia (SCH) (n = 237) or bipolar I disorder (BD-I) (n = 177), were prescribed aripiprazole (10 mg, 15 mg and 30 mg) independently of the study, in accordance with the approved SmPC. Data collection took place at the time of patient enrolment and subsequently after one and three months. Patient adherence was assessed by the treating physicians and also by the patients, using a self-report questionnaire (Morisky Green Levine / MGL). The severity of the disease was evaluated using the Clinical Global Impression – Severity (CGI-S) scale, while the changes in severity were measured with the Clinical Global Impression – Improvement (CGI-I) scale. Cognitive function was assessed based on the cognition/disorganization components of the Positive and Negative Syndrome Scale (PANSS).
Results: Of the 414 patients, 99.3% remained on aripiprazole therapy throughout the 12-week study period, with treatment discontinued in only three cases. In the overall population, the treating physicians classified patient adherence to aripiprazole therapy as ‘seemingly trouble-free’ in 74.8% of cases after one month (SCH: 73.3%, BD-I: 76.8%) and 76.8% after three months (SCH: 72.9%, BD-I: 82.2%). Based on the MGL selfreport adherence questionnaire, 55.4% of patients (SCH: 56.5%, BD-I: 53.8%) were categorized as having ‘high adherence’ after one month, increasing to 57.2% after three months (SCH: 54.9%, BD-I: 60.5%). Overall, 76% of patients were treated with aripiprazole in monotherapy. 29% of patients with schizophrenia and 18% of patients with bipolar I disorder received combination therapy with another antipsychotic. Additionally, 51% of patients with bipolar I disorder received concomitant mood stabilizer treatment. According to CGI-I scores, 74.1% of patients ‘much improved’ or ‘very much improved’ after three months. Gradual improvement was also observed in both patient groups in the cognition/disorganization components of the PANSS scale. Overall, aripiprazole was well tolerated by the patients. Adverse events were reported in 10 cases, all of which were predominantly mild. No aripiprazole blood level monitoring was conducted during the study.
Conclusions: In outpatient care, the observed real-world efficacy, favourable adverse events profile, good tolerability, and the strengthened doctor-patient relationship under real-life settings may have collectively contributed to the higher-than-expected treatment persistence, sustained medication adherence, and consequently, good efficacy. Aripiprazole blood level monitoring and the associated personalised treatment approach are currently not part of routine clinical practice in Hungary.
(Neuropsychopharmacologia Hungarica Supplement 2024; 26: 2–19)
Introduction
Although the range of available antipsychotics has steadily expanded since the 1950s, the treatment of psychoses, such as schizophrenia and bipolar disorder remains an ongoing challenge.
Aripiprazole was first approved for the treatment of schizophrenia in the United States in 2002, and its efficacy was later demonstrated in the management of bipolar I disorder as well.
In Hungary, aripiprazole is indicated for the treatment of moderate to severe manic episodes in patients with schizophrenia and bipolar I disorder, and for the prevention of new manic episodes in patients with bipolar I disorder who experienced predominantly manic episodes.
From a pharmacodynamic perspective, aripiprazole differs from other antipsychotics primarily due to its partial agonistic effect on D2 receptors, with relatively low intrinsic activity, thereby exerting a stabilising effect on dopamine neurotransmission. Additionally, it has significant binding affinity for the serotonin 5-HT2A receptor (Citrome, 2006; Kikuchi et al., 2021).
In this study, we aimed to collect real-world data on the experiences with aripiprazole treatment in different diagnostic groups, with the involvement of psychiatrists as investigators in daily practice.
Since medication adherence is crucial in both schizophrenia and bipolar disorder for preventing relapses, repeated episodes, their severity, and hospitalizations, as well as remission, residual symptoms, psychosocial impairment, and quality of life (Sümegi, 2014; Erdélyi-Hamza et al., 2021), we examined patient adherence to treatment as a primary endpoint, along with the proportion of patients who remained on therapy at the end of the third month.
Our objectives also included analysing patient population patterns, understanding therapeutic decision-making, assessing the real-world effectiveness of the treatment, evaluating the development of leading and cognitive symptoms, and examining the safety profile of the medication.
Additionally, we aimed to assess the possibilities and practices of personalised treatment, including aripiprazole blood level monitoring.
Methods – study design
The open-label, multicentre, prospective, non-interventional ARIAD study included patients aged 18 years and older, diagnosed with schizophrenia or bipolar I disorder, treated with aripiprazole tablets of various strengths (Arisppa® 10 mg, 15 mg, 30 mg; Krka’s medicines are marketed in different countries under different brand names) according to the indication specifications in the product’s Summary of Product Characteristics (SmPC). The medication was used either as monotheraphy or in combination with other antipsychotics.
Exclusion criteria included contraindications specified in the product’s SmPC, as well as the presence of a serious medical condition that would have prevented participation in the study. Patients who were under full guardianship limiting their legal capacity, or partial guardianship regarding healthcare-related rights or certain financial matters (as defined by Article 159 of Act CLIV of 1997), were not eligible for inclusion.
Written informed consent to participate in the study was obtained from all patients. The study protocol was approved by the National Institute of Pharmacy and Nutrition (OGYÉI) in their decision No. 51707-6/2020.
The study was sponsored by KRKA Magyarország Kft.
Data collection, analyses
Data collection occurred three times during the three-month follow-up: at the time of enrolment, and then one and three months after the first data collection.
Although data collection during in-person visits was preferred in all cases, if the epidemic situation only allowed for remote data collection, the second and third data collections could also be conducted remotely.
Data regarding the patients’ demographics, clinical information, comorbidities, concomitant medications, psychiatric history and symptoms, patient adherence, and the patients’ condition and treatment were collected by the investigators during all three data collection points and recorded on an electronic case report form (eCRF).
The patients’ data were also in part evaluated separately based on different diagnostic groups, therapeutic targets (schizophrenia or bipolar I disorder, and within that, the treatment of mania or prevention of a new manic episode), and therapeutic strategies (monotherapy or combination antipsychotic therapy).
The patients’ adherence to the medication was assessed based on evaluations from both the physicians and the patients themselves.
The physicians assessed the patients’ adherence to medication after one and three months by selecting one of four response options: Administration of the medication is seemingly problemfree; It is sometimes uncertain, based on specific questioning; The patient spontaneously reports having difficulty in taking the medication; The patient is assumed to take their medication in a noncompliant manner. They also had the option to select the option ‘Not assessed’.
The patients themselves assessed their adherence after one and three months using the MGL fouritem self-report questionnaire (Morisky et al., 1986). A validated Hungarian translation of the questionnaire was used in the study with the permission of the copyright holder. The questionnaire included four questions: Do you ever forget to take your medicine? Are you careless at times about taking your medicine? When you feel better, do you sometimes stop taking your medicine? Sometimes if you feel worse when you take the medicine, do you stop taking it? Adherence was categorized as high for zero ‘yes’ responses, medium for 1–2 ‘yes’ responses, and low for 3–4 ‘yes’ responses.
The severity of the illness was assessed by the physician for each patient at all three data collection points. The evaluation was based on the symptoms, behaviour, and functions present during the study period, using the Clinical Global Impression – Severity (CGI-S) scale, which consists of seven levels with the following scores: 1 = normal, not at all ill, 2 = borderline mentally ill, 3 = mildly ill, 4 = moderately ill, 5 = markedly ill, 6 = severely ill, 7 = among the most extremely ill patients.
The change in disease severity compared to baseline was assessed after one and three months using the Clinical Global Impression-Improvement (CGI-I) scale: 1 = very much improved, 2 = much improved, 3 = minimally improved, 4 = no change, 5 = minimally worse, 6 = much worse, 7 = very much worse (Busner & Targum, 2007).
At the baseline, physicians selected the three leading symptoms for each patient from the DSM-5 list of the most typical symptoms and determined their severity on a scale of 1 to 10.
Any changes in leading symptoms were assessed after one and three months.
Cognitive function was evaluated in both schizophrenia and bipolar I disorder patients using the cognition/disorganization components of the PANSS scale, including: conceptual disorganization, difficulty in abstract thinking, poor attention (PANSS P2, N5, G11) (Wallwork et al., 2012, Rodriguez Jimenez et al., 2013). Although the 30-item PANSS scale was developed for monitoring symptoms of schizophrenia, it is also used to measure symptom changes in bipolar and schizoaffective disorders (McIntyre et al., 2023; Anderson et al., 2017).
At the end of the 3-month treatment period, the investigators separately evaluated the changes in general cognitive functioning, social behaviour/relationships, and overall well-being on a 7-point scale similar to the CGI-I, ranging from ‘very much improved’ to ‘very much worsened’. Adverse events were collected and evaluated throughout the entire study period.
Statistical analysis
The recorded data were analysed using a free, open-source statistical software (R program). Descriptive statistical methods (frequency and percentage distribution for categorical variables; mean and standard deviation for continuous variables) were applied separately for each treatment group (monotherapy or combination therapy), for each dose (10 mg, 15 mg and 30 mg), and for each data collection point (first, second and third). Percentages were rounded to whole numbers. Chisquared test was used to assess the differences between monotherapy and combination therapy groups (p < 0.05 was considered significant). Unpaired t-test was used to compare disease severity and changes in condition at each data collection point between groups using the medication for manic episode treatment and new manic episode prevention.
Results
Patients enrolled
A total of 414 patients were enrolled in the study, including 259 women (63%) and 155 men (37%). Among them, 237 patients (59% women, 41% men) were diagnosed with schizophrenia, while 177 patients (67% women, 33% men) were diagnosed with bipolar I disorder. The average age of the patients was 46 (±14) years. The presence of comorbid mental illness or psychiatric comorbidity was reported in 29% of the patients (SCH: 32%, BD-I: 24%). Anxiety was reported as the most prevalent comorbidity. This affected 101 individuals (24%) in the overall population, 64 individuals (27%) among patients with schizophrenia, and 37 individuals (21%) among those with bipolar I disorder. Comorbid ADHD was reported in 3 patients (SCH: 2, BD-I: 1), and alcohol or medication dependency in 8 patients (SCH: 3, BD-I: 5).
Hypertension was reported in 13% of cases, hyperlipidaemia in 6%, and type II diabetes mellitus in 4%. No significant differences were observed between patient groups in terms of physical parameters and the prevalence of these comorbid conditions.
In the case of schizophrenia, 29% of patients received combination antipsychotic treatment, while in the case of bipolar I disorder, 18% received such treatment. The proportion of comorbidities was moderately higher among those receiving combination antipsychotic treatment compared to those on aripiprazole antipsychotic monotherapy in both the SCH and BD-I patient groups.
The average duration of diagnosis at the time of the first data collection was 12 (±10) years for the overall population, 14 (±11) years for the group with schizophrenia, and 9.4 (±8.9) years for the group with bipolar I disorder.
Adherence
Therapy persistence/Time spent on therapy
Of the 414 patients, 99% remained on aripiprazole therapy throughout the 12-week study period, with treatment discontinued in only three cases.
Patient adherence based on the physician’s assessment
When examining the entire patient population, the treating physicians categorised more than 90% of patients in all groups, both after one and three months, as either ‘seemingly problem-free’ or ‘administration of the medication is sometimes uncertain’.
- 75% and 77% of patients were included in the ‘seemingly problem-free’ group after one month and three months, respectively.
- In approximately 2% of cases, the treating physician assessed that the patient was likely not taking the medication correctly, both after one month and three months.
- After one and three months, the physicians’ assessment remained essentially unchanged for 79% of the patients. The distribution of responses for the two diagnostic groups separately is presented in Table 1.
Patient adherence according to patients’ assessment (MGL self-report questionnaire)
The self-report questionnaire was completed after one month and after three months by 316 and 313 patients, respectively.
After one month, 55% of patients (SCH: 57%, BD-I: 54%) were categorized in the high adherence category, 39% (SCH: 40%, BD-I: 38%) in the medium adherence category, and 6% (SCH: 4%, BD-I: 8%) in the low adherence category, while after three months, 57% of patients (SCH: 55%, BD-I: 61%) were categorized in the high adherence category, 34% (SCH: 38%, BD-I: 29%) in the medium adherence category, and 9% (SCH: 7%, BD-I: 11%) in the low adherence category.
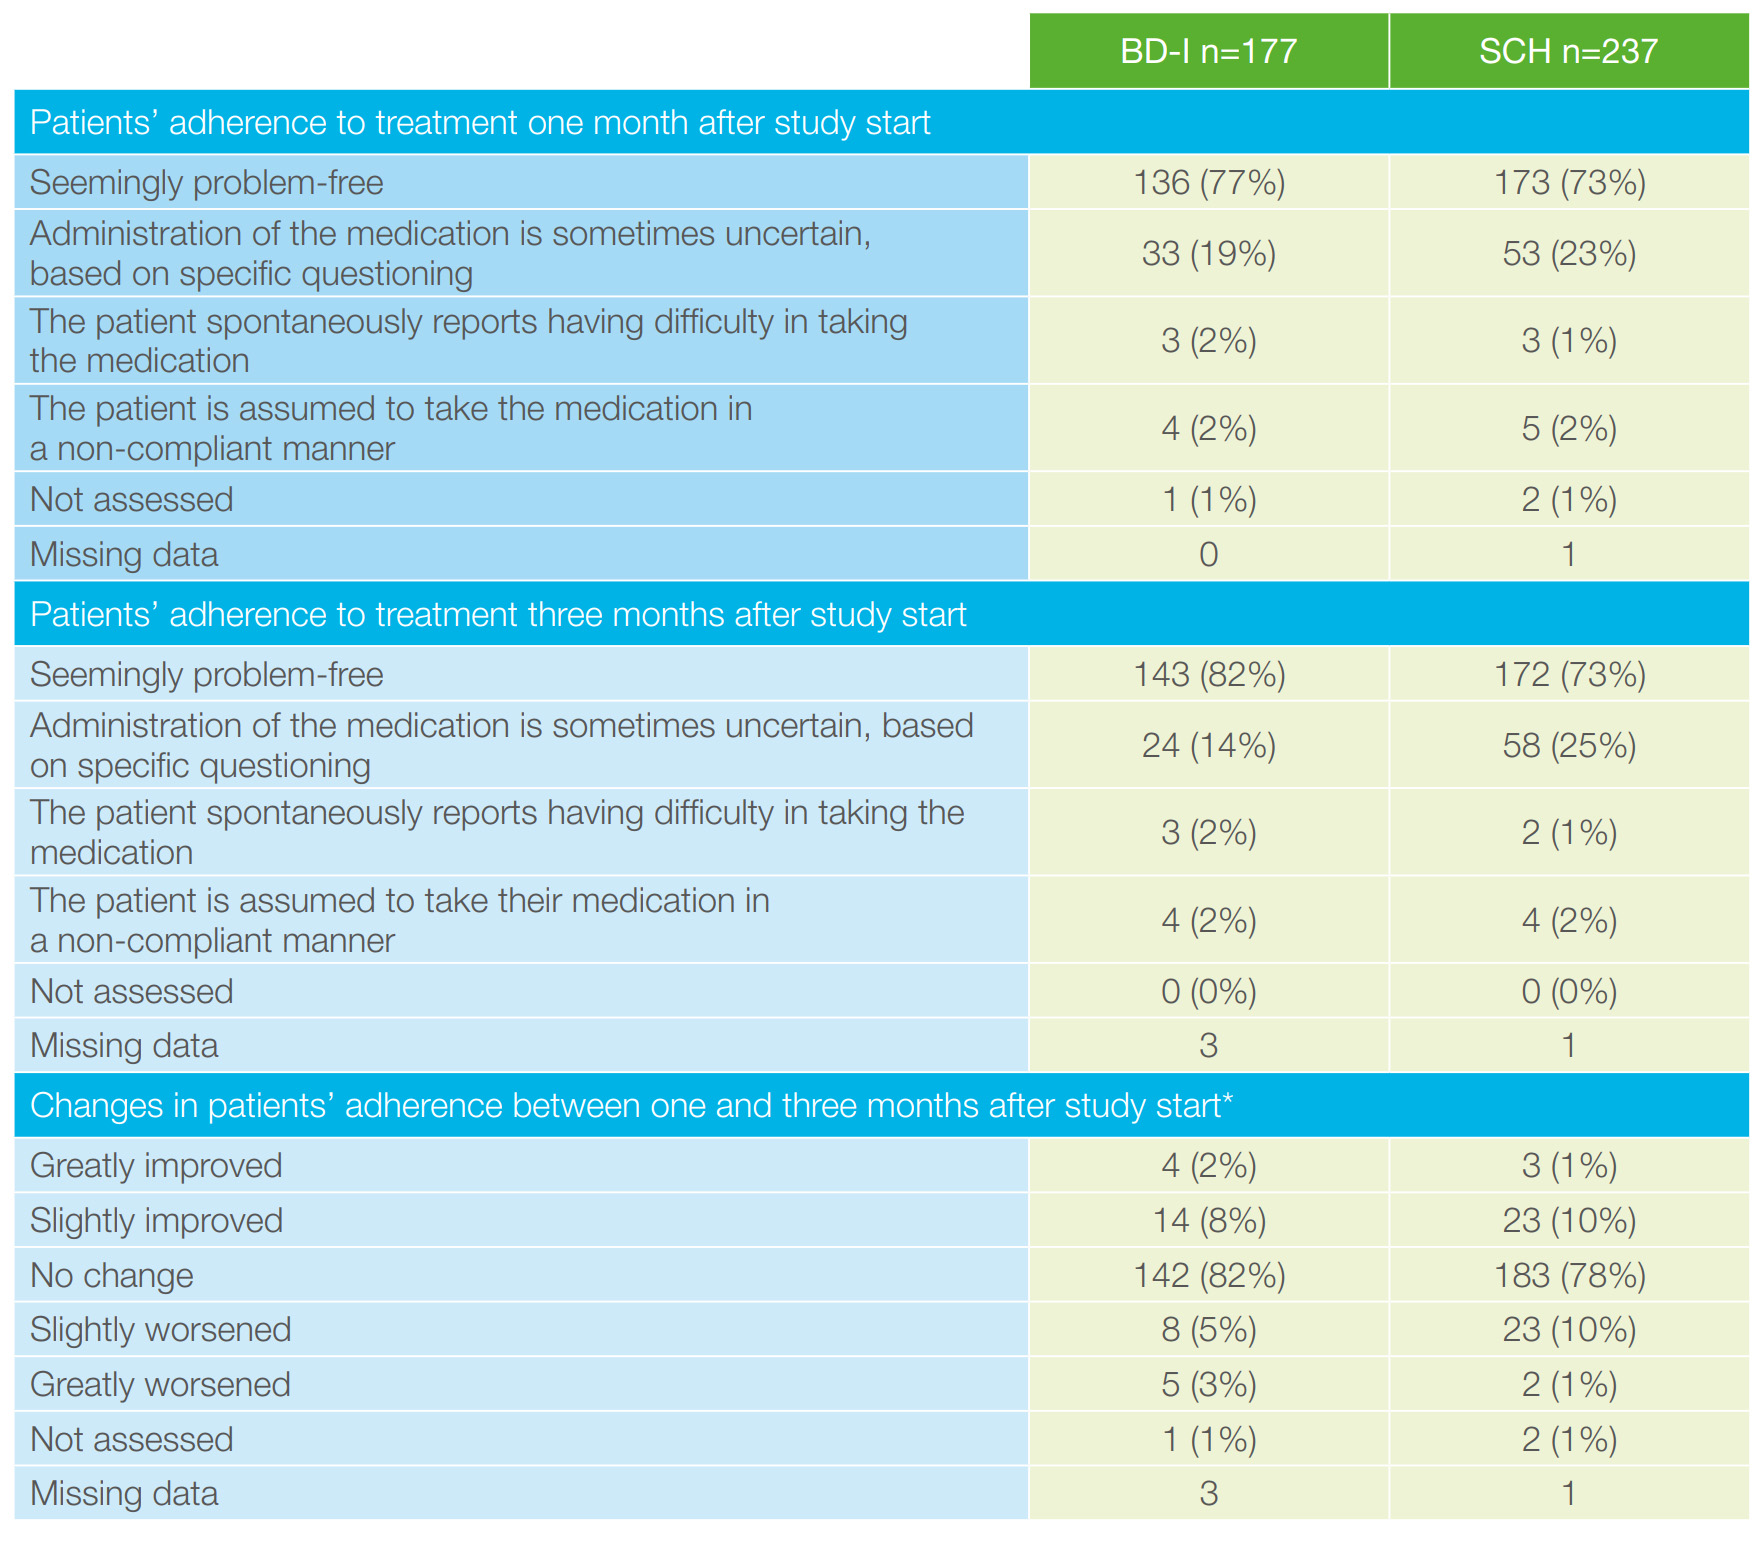
Table 1 Patient adherence to aripiprazole treatment as assessed by investigators in the two diagnostic groups (BD-I and SCH)
*Assessment after three months compared to after one month of study inclusion:
‘Greatly improved’ = improved by at least 2 grades; ‘Slightly improved’ = improved by 1 grade
‘No change’ = unchanged; ‘Slightly worsened’ = worsened by 1 grade, ‘Greatly worsened’ = worsened by at least 2 grades.
If the response was ‘Not assessed’ at any data collection point, the difference was also recorded as ‘Not assessed’.
Historical patient data
History of patients with schizophrenia
By the time of enrolment in the study, 175 patients with schizophrenia (74%) had already experienced at least two relapses. 159 patients had been on antipsychotic treatment for more than three months. In relation to the episode/treatment period under investigation (within a maximum of six months, but not applied at the time of study enrolment), 64 patients had received other antipsychotic treatment, mostly for longer than three months. The most commonly used active substances were olanzapine, quetiapine, paliperidone, or risperidone. The most common reasons for discontinuing these medications were adverse events and lack of adequate efficacy (both in 39% of cases).
History of patients with bipolar I disorder
By the time of study entry, 117 patients (66%) had experienced two or more manic episodes, and 128 patients (72%) had experienced two or more depressive episodes. Nearly 70% of patients had a history of mixed episodes.
96 patients had previously undergone antipsychotic treatment (not related to the current episode), with the duration exceeding three months in most cases. In connection with the episode/treatment period under investigation (within a maximum of six months, but not applied at the time of study entry), 36 patients had received other antipsychotic treatment, mostly quetiapine or olanzapine. In more than half of the cases, the treatment duration exceeded three months.
The most common reasons for discontinuing these medications were adverse events (40% of cases) and lack of adequate efficacy (32% of cases).
Medication
Medication decisions for patients with schizophrenia
At the start of the study, 32% of patients with schizophrenia received aripiprazole at a 10 mg dose, 47% at a 15 mg dose, and 21% at a 30 mg dose.
A total of 169 patients (71%) received aripiprazole monotherapy without additional antipsychotic treatment, while 68 patients (29%) were also treated with another antipsychotic, most commonly olanzapine (16), quetiapine (13), and clozapine (13).
In addition to antipsychotic therapy, a significant proportion of patients also received other psychotropic medications on a regular basis, with 81 patients receiving anxiolytics/sleep aids, 43 receiving antidepressants, and 9 receiving mood stabilisers.
Changes in medication
At the time of the second and third data collection, 236 patients with schizophrenia were still on aripiprazole treatment. Only in one case was the treatment discontinued before the second data collection, based on the patient’s decision.
The aripiprazole dose initially prescribed was adjusted in 27 patients (11%) after one month and in another 27 patients (11%) after three months. The proportion of medications shifted slightly towards those with higher active ingredient content (Figure 1).
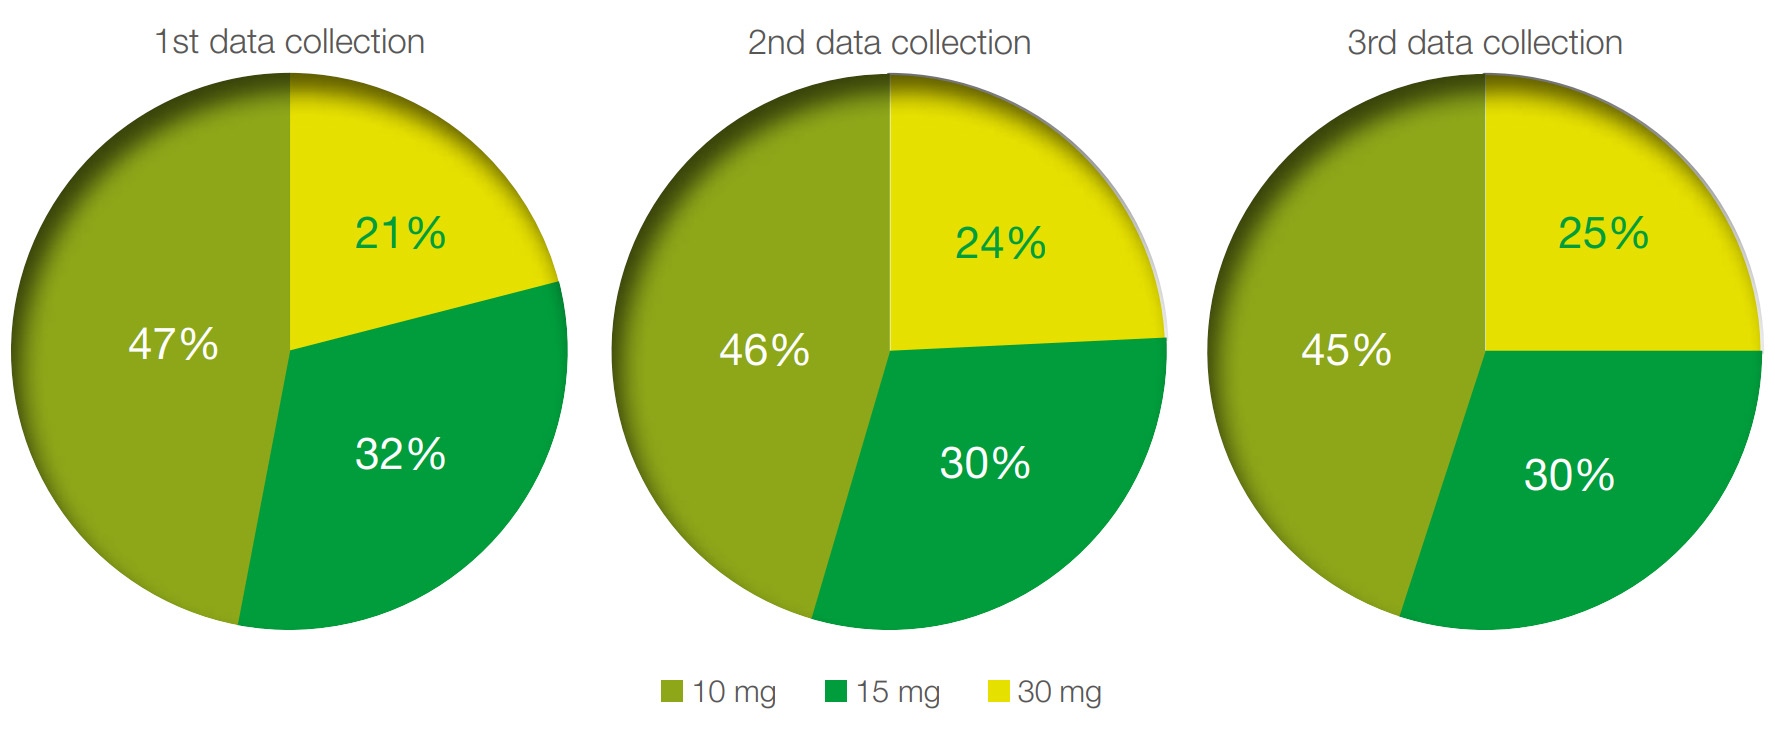
Figure 1 Aripiprazole therapy administered at baseline and after the first month and the third month among patients with schizophrenia
Medication decisions for patients with bipolar I disorder
In 98 cases (58%), the indication for treatment was the management of a manic episode, while in 72 cases (42%), it was the prevention of a new manic episode. In 7 cases, the physician did not specify a more precise treatment goal beyond the indication of bipolar I disorder.
At the start of the study, 49% of patients received aripiprazole at a 10 mg dose, 38% at a 15 mg dose, and 14% at a 30 mg dose.
A total of 145 patients (82%) did not receive any additional antipsychotic treatment alongside aripiprazole, while 32 patients (18%) were also treated with other antipsychotic medications, most commonly quetiapine (11 patients) and olanzapine (9 patients).
In addition to antipsychotic therapy, a significant proportion of patients regularly received other psychotropic medications: 90 patients were on mood stabilisers, 71 on anxiolytics/sleep aids, and 53 on concomitant antidepressant treatment.
Changes in medication
After one month, all 177 patients remained on aripiprazole therapy. By the end of the third month, treatment was discontinued in two patients. Thus, the therapy persistence rate was nearly 99%. The reasons for discontinuation were adverse events in one case (intensification of depersonalizationderealization experiences) and lack of patient cooperation (non-compliance) in the other case. The dose of the aripiprazole preparation set at the beginning of the study was adjusted in 26 patients (15%) after one month and in an additional 13 patients (7%) after three months. The proportion of medications shifted towards those with higher active ingredient content (Figure 2).
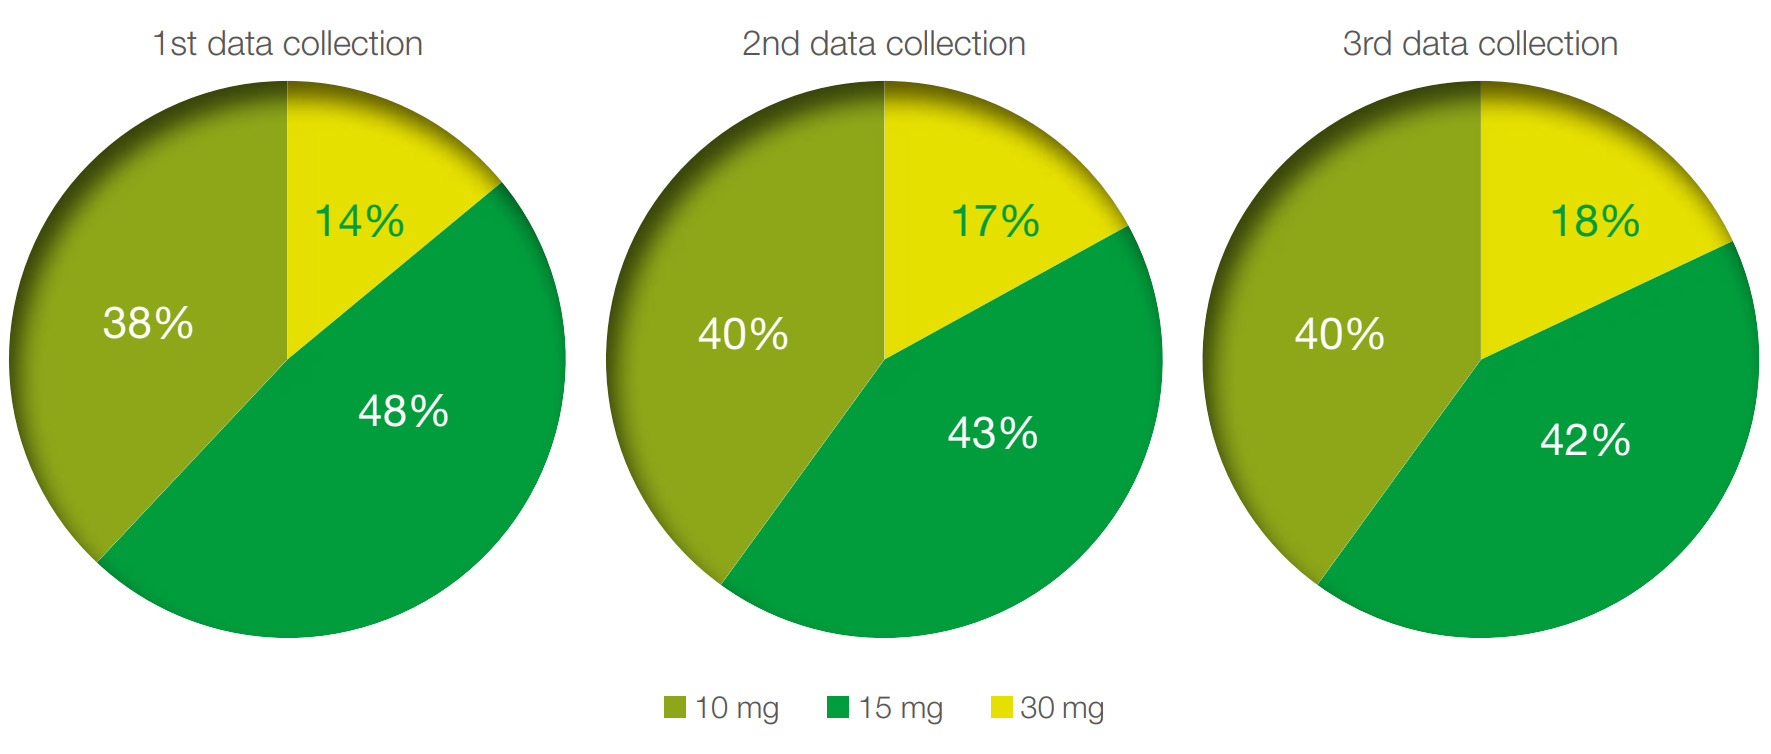
Figure 2 Aripiprazole therapy administered at baseline and after the first and the third month among patients with bipolar I disorder
Other concomitant antipsychotic therapy in patients with schizophrenia
In the study, 29% of patients with schizophrenia (68 individuals) received combination antipsychotic therapy.
In the first month, discontinuation of a concomitant antipsychotic was reported in 13 cases, with an additional discontinuation of one patient by the end of the third month. In most cases, the discontinuation of the antipsychotic in the first month was due to cross-titration/medication switch.
Dose adjustments of concomitant antipsychotics were recorded for five patients by the second data collection point, and for an additional three patients by the third data collection point. A new antipsychotic was prescribed in three cases after the first month.
Among other concomitantly used psychotropic medications, discontinuation, dose adjustment, or new prescription was reported in a negligible number of cases (2–3 cases).
Antipsychotic mono- or combination therapy
In the group receiving combination therapy, the number of previous relapses was significantly higher (p = 0.04), and the duration of previous antipsychotic treatment unrelated to the current episode was longer (p < 0.001) compared to the monotherapy group. There was no significant difference in the presence of previous antipsychotic treatment unrelated to the current episode, but there was a significant difference in the presence of treatment related to the current episode. In the combined treatment group, significantly more cases involved the use of an antipsychotic that had already been discontinued at the time of inclusion (p < 0.01).
Other concomitant antipsychotic therapy in patients with bipolar I disorder
The group receiving combination antipsychotic therapy included 18% of patients (32) with bipolar I disorder.
In the first month, discontinuation of a concomitant antipsychotic was reported in four cases, with an additional one case of discontinuation reported by the end of the third month.
Dose adjustments of concomitant antipsychotics were recorded for in one patient each by the second and third data collection points.
Antipsychotic mono- or combination therapy
In the combination therapy group, the proportion of patients with a history of antipsychotic use (unrelated to the current episode) was significantly higher than in the monotherapy group (25 yes/3 no compared to 71 yes/59 no; p < 0.001).
Effectiveness
Disease severity based on CGI-S at each data collection point
The average disease severity decreased from visit to visit in both patient groups.
Among patients with schizophrenia:
The investigators reported CGI-S scores for 232 cases during the first data collection, 224 cases during the second, and 209 cases during the third data collection.
No patients were classified as ‘normal, not ill at all’ either at inclusion or one month later, but 5% were classified as such after three months.
The proportion of ‘mildly ill’ patients increased from 7% to 26%, and then to 52%. The ‘moderately ill’ category included 50% of patients at the first data collection, which increased to 63% one month later, and then to 42% by the end of the third month. The proportion of ‘markedly ill’ patients decreased from 35% to 11%, and then to 1%, while the proportion of ‘severely ill’ patients decreased from the initial 9% to 0% by the end of the first month and remained unchanged until the third month. No patients were classified as ‘borderline mentally ill’ or ‘among the most severely ill’.
The average CGI-S score decreased from 4.45 (±0.75) to 3.86 (±0.61) after one month, and then to 3.33 (±0.75) after three months (Figure 3).
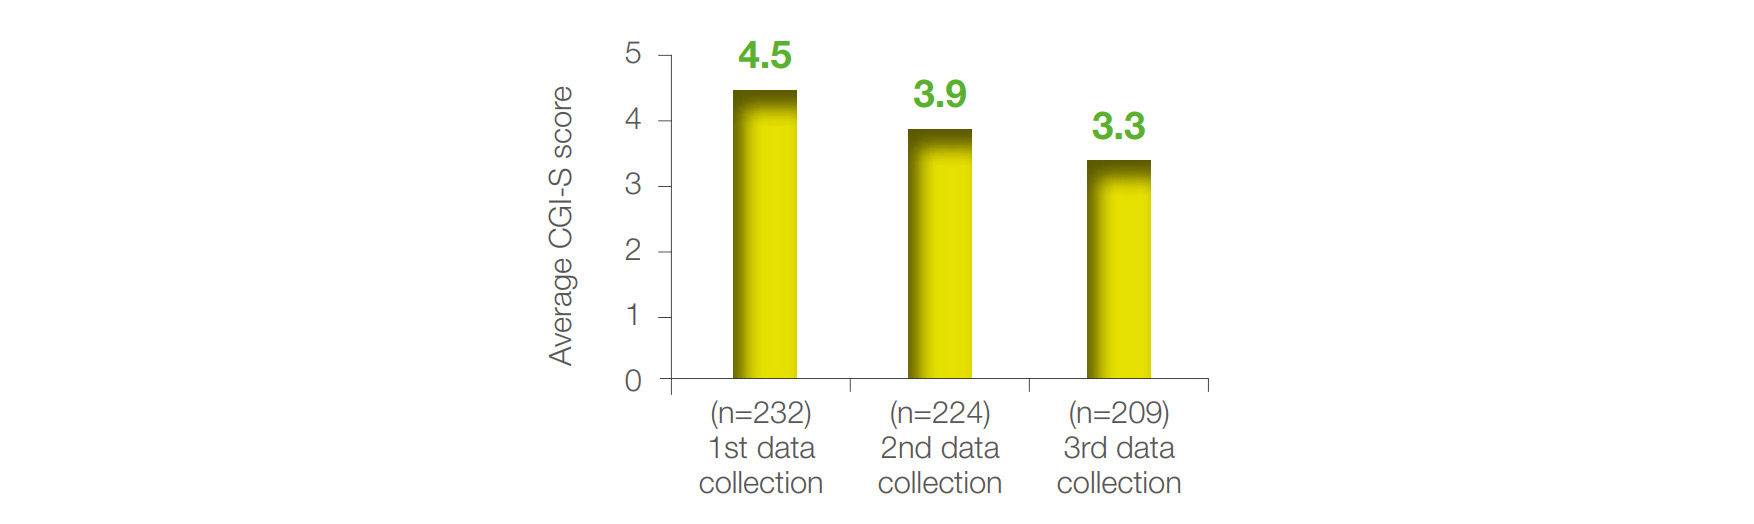
Figure 3 CGI-S average scores at baseline and at second and third data collection points among patients with schizophrenia
Among patients with bipolar I disorder:
The investigators reported CGI-S scores for 175 cases during the first, 168 cases during the second, and 128 cases during the third data collection.
At inclusion, 1% of patients were classified as ‘normal, not at all ill,’ which increased to 4% after one month and to 18% after three months. The proportion of ‘mildly ill’ patients increased from 6% to 43%, and then to 57%. The ‘moderately ill’ category included 49% of patients at both the first and second data collection points, and 22% at the third data collection point. The proportion of ‘markedly ill’ patients decreased from 39% to 4%, and then to 3%, while the proportion of ‘severely ill’ patients decreased from the initial 5% to 0% after one month and remained unchanged. No patients were classified as ‘borderline mentally ill’ or ‘among the most severely ill’. The average CGI-S score decreased from 4.38 (±0.77) to 3.5 (±0.74) after one month, and then to 2.92 (±1.03) after three months (Figure 4).
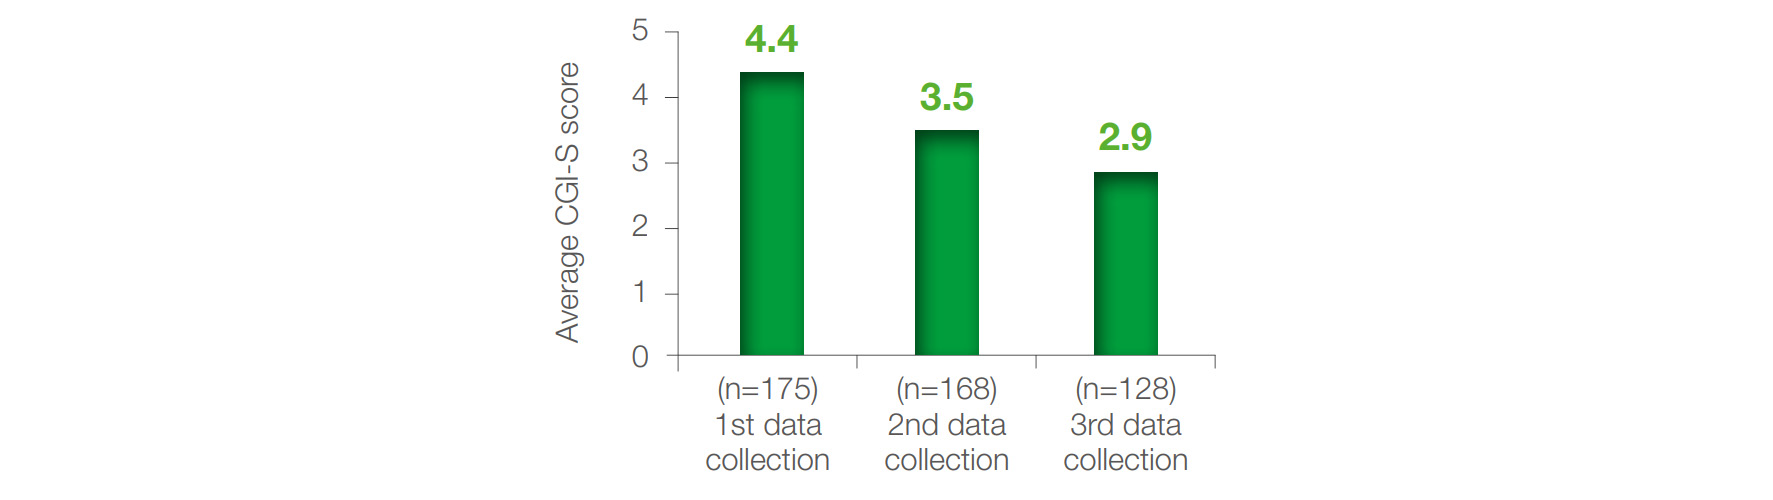
Figure 4 CGI-S average scores at baseline and at second and third data collection points in among patients with bipolar I disorder
Change in disease severity based on CGI-I scores at the second and the third data collection points
Based on the CGI-I scale data after one month (second data collection point: n = 236), 89% of patients with schizophrenia showed improvement (very much improved: 4%, much improved: 30%, minimally improved: 55%, no change: 11%). After three months (third data collection point n = 235), 96% of patients had improved, with the proportion of patients reporting ‘very much improved’ and ‘much improved’ further increasing (very much improved: 24%, much improved: 45%, minimally improved: 27%, no change: 3%) (Figure 5).
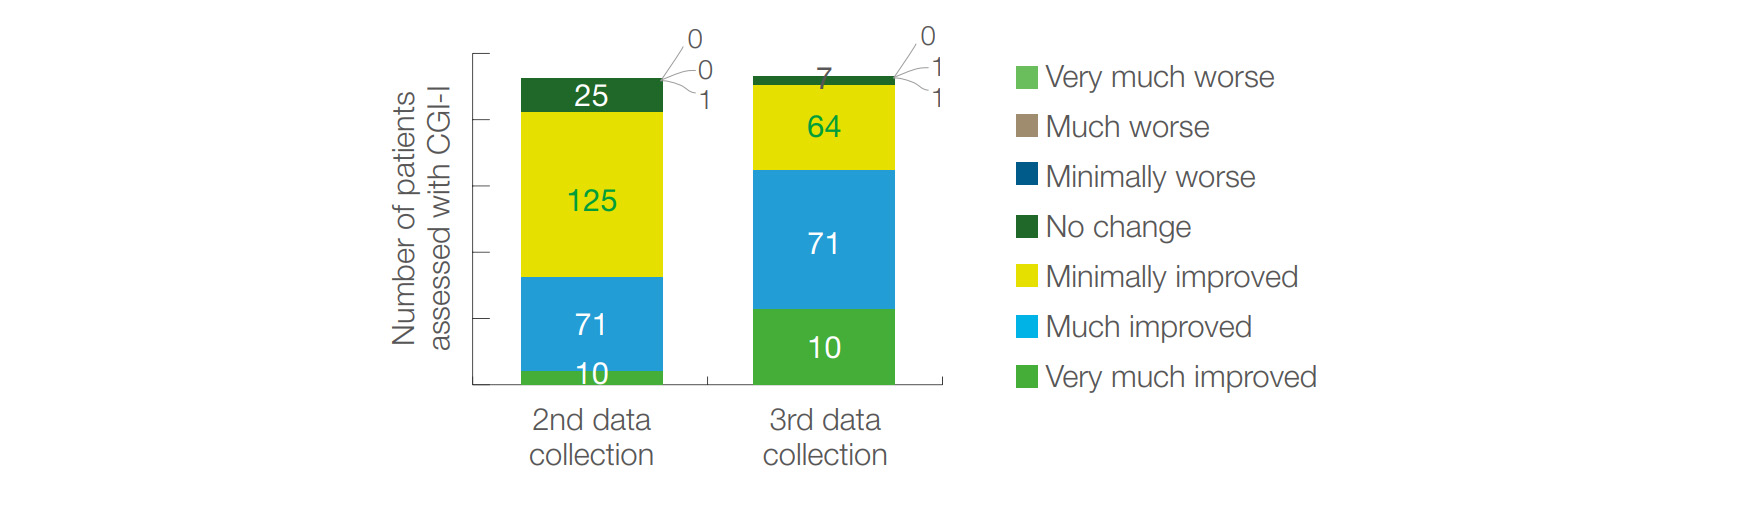
Figure 5 Change in patient’s condition based on physician’s assessment (CGI-I) among patients with schizophrenia
Deterioration in condition was reported for one patient at the second data collection point, and for two patients at the third data collection point.
The average CGI-I score was 2.73 (±0.72) at the second data collection point, and 2.12 (±0.85) at the third data collection point.
In the group of patients with bipolar I disorder, according to the CGI-I scale data after one month, 93% of the patients showed improvement in their condition (very much improved: 10%, much improved: 47%, slightly improved: 36%, unchanged: 6%). After three months, 97% of patients had improved, with the proportion of patients reporting ‘very much improved’ and ‘much improved’ further increasing (very much improved: 33%, much improved: 48%, minimally improved: 16%, no change: 2%). No deterioration was reported at the second data collection point, but one patient experienced worsening at the third data collection point (Figure 6).
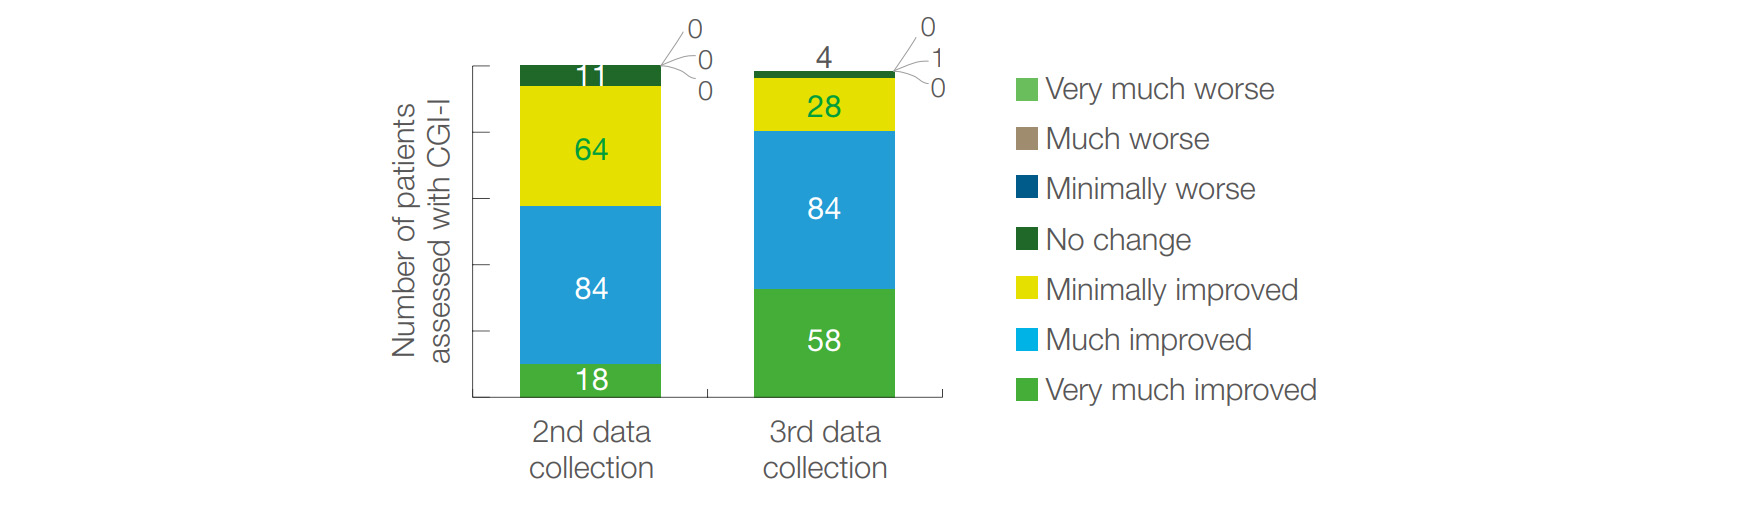
Figure 6 Change in patient’s condition based on physician’s assessment (CGI-I) among patients with bipolar I disorder
The average CGI-I score was 2.38 (±0.75) at the second visit, and 1.90 (±0.82) at the third visit. The extent of change in condition, expressed by the CGI-I score, did not differ significantly after one month between patients who receive treatment for a manic episode and those treated to prevent a new manic episode. However, after three months, the degree of improvement in the manic group was significantly higher than in the prevention group (1.79 ±0.75 compared to 2.04 ±0.87, p = 0.049).
Leading symptoms and their changes
Leading symptoms and their changes among patients with schizophrenia
In the 237 patients with schizophrenia, the treating physicians identified two or three leading symptoms per patient (a total of 585 symptoms) at the first data collection point. The severity of these symptoms was rated on a scale of 1 to 10. The most frequently reported symptoms were negative symptoms and delusions (Table 2).
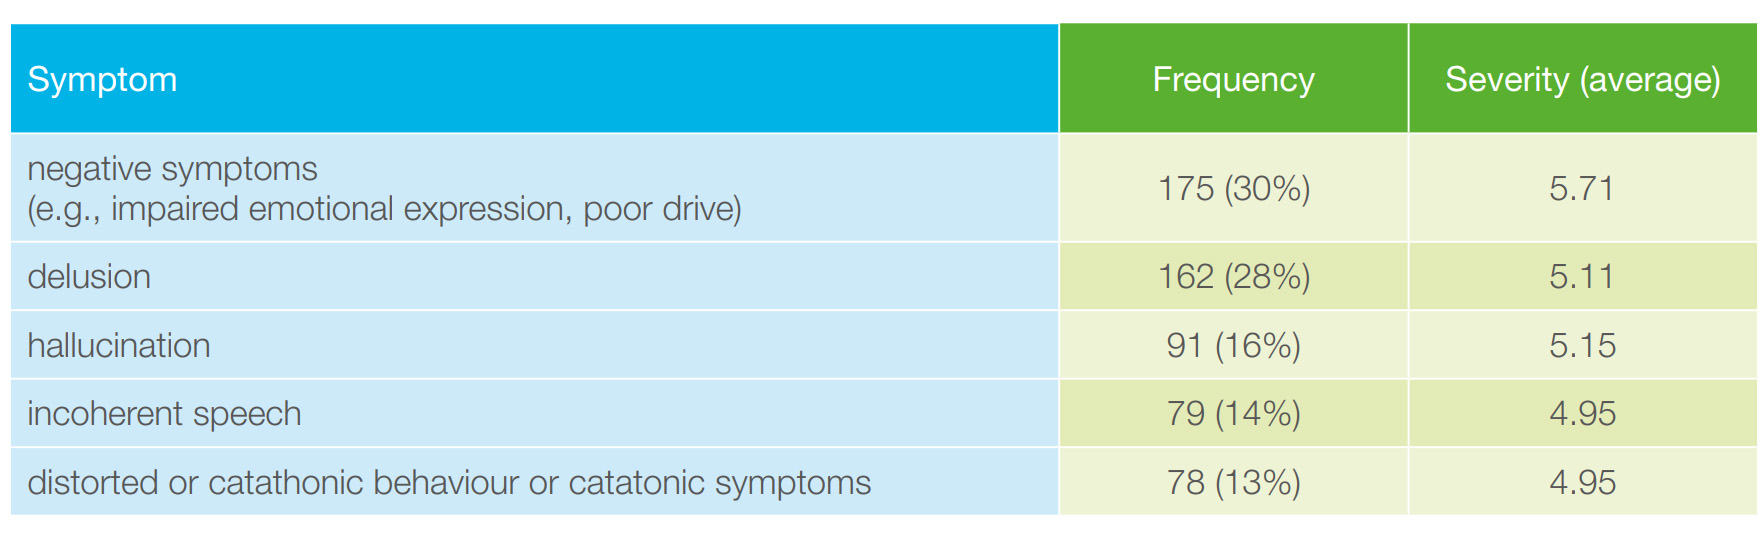
Table 2. Leading symptoms at the start of the study based on physician’s assessment among patients with schizophrenia
One and three months after the study began, physicians provided information on the frequency and severity of 471 leading symptoms. After one month, more than 78% of the symptoms showed at least minimal improvement; after three months, 94% of the symptoms showed at least minimal improvement (Figure 7) compared to baseline. Only in two cases was worsening of a leading symptom reported.
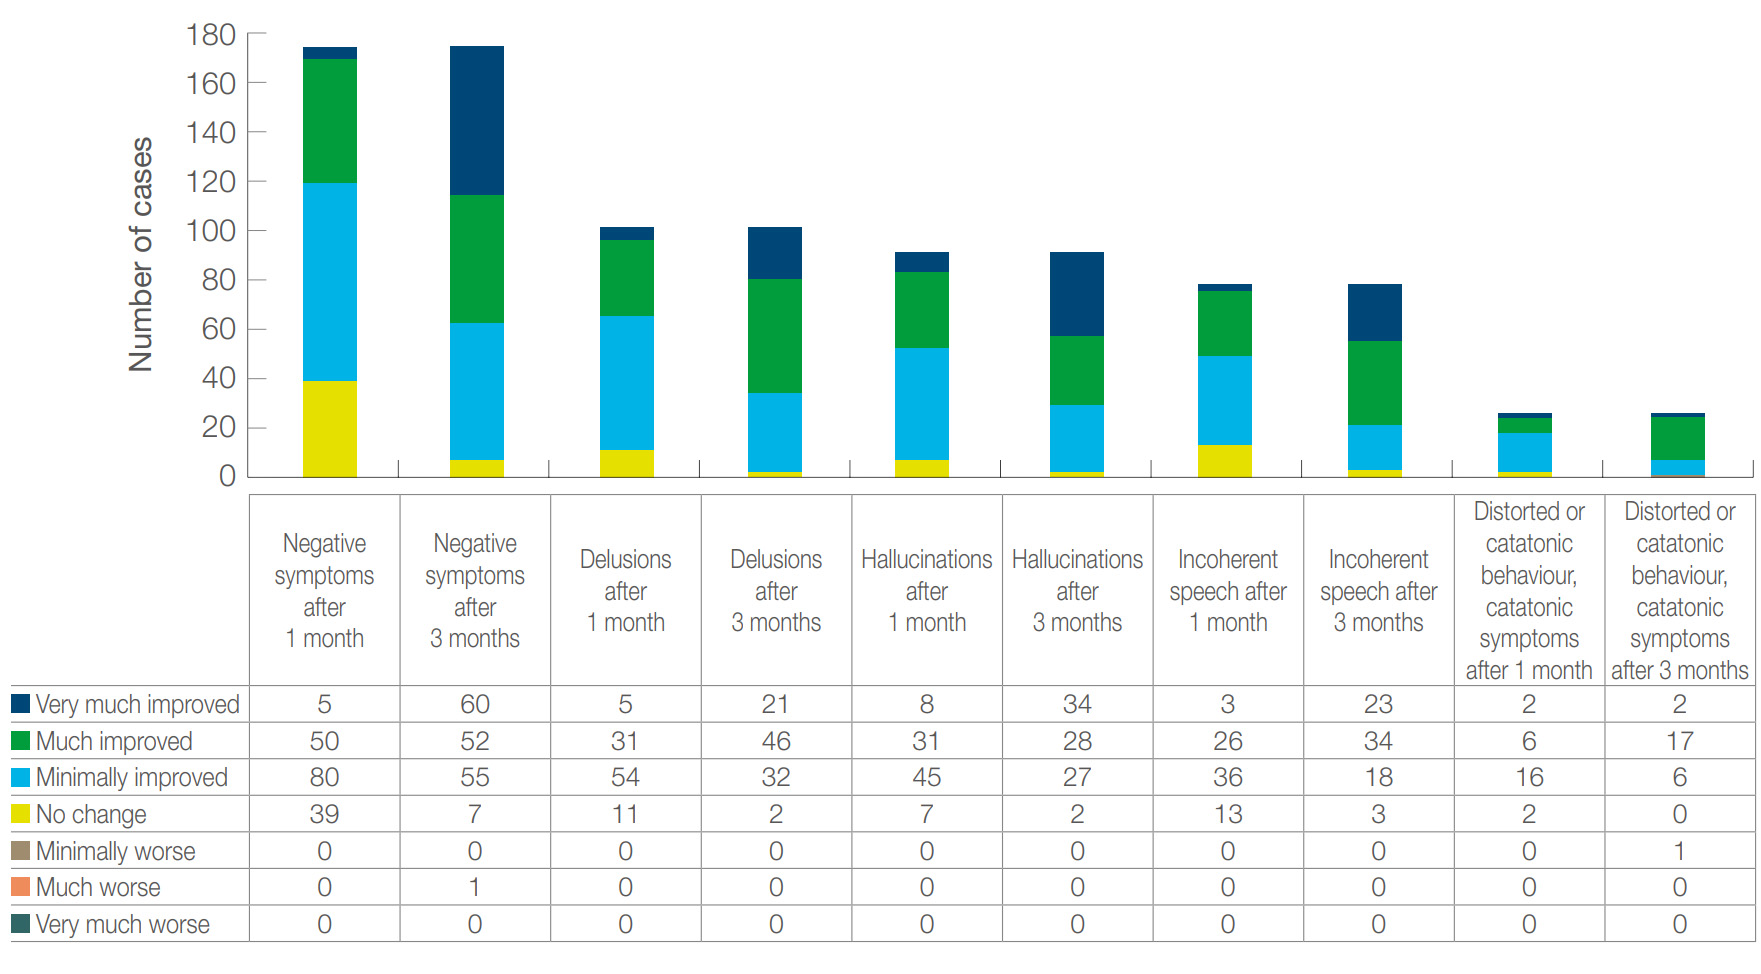
Figure 7 Changes in leading symptoms (n = 471) from the start of the study to the end of the first month and third month among patients with schizophrenia
Leading symptoms and their changes among patients with bipolar I disorder
In the 177 patients with bipolar I disorder, the treating physicians identified two or three leading symptoms per patient (a total of 355 symptoms) at the first data collection point. The severity of these symptoms was rated on a scale of 1 to 10.
The most commonly reported symptoms were reduced need for sleep and irritability (Table 3).
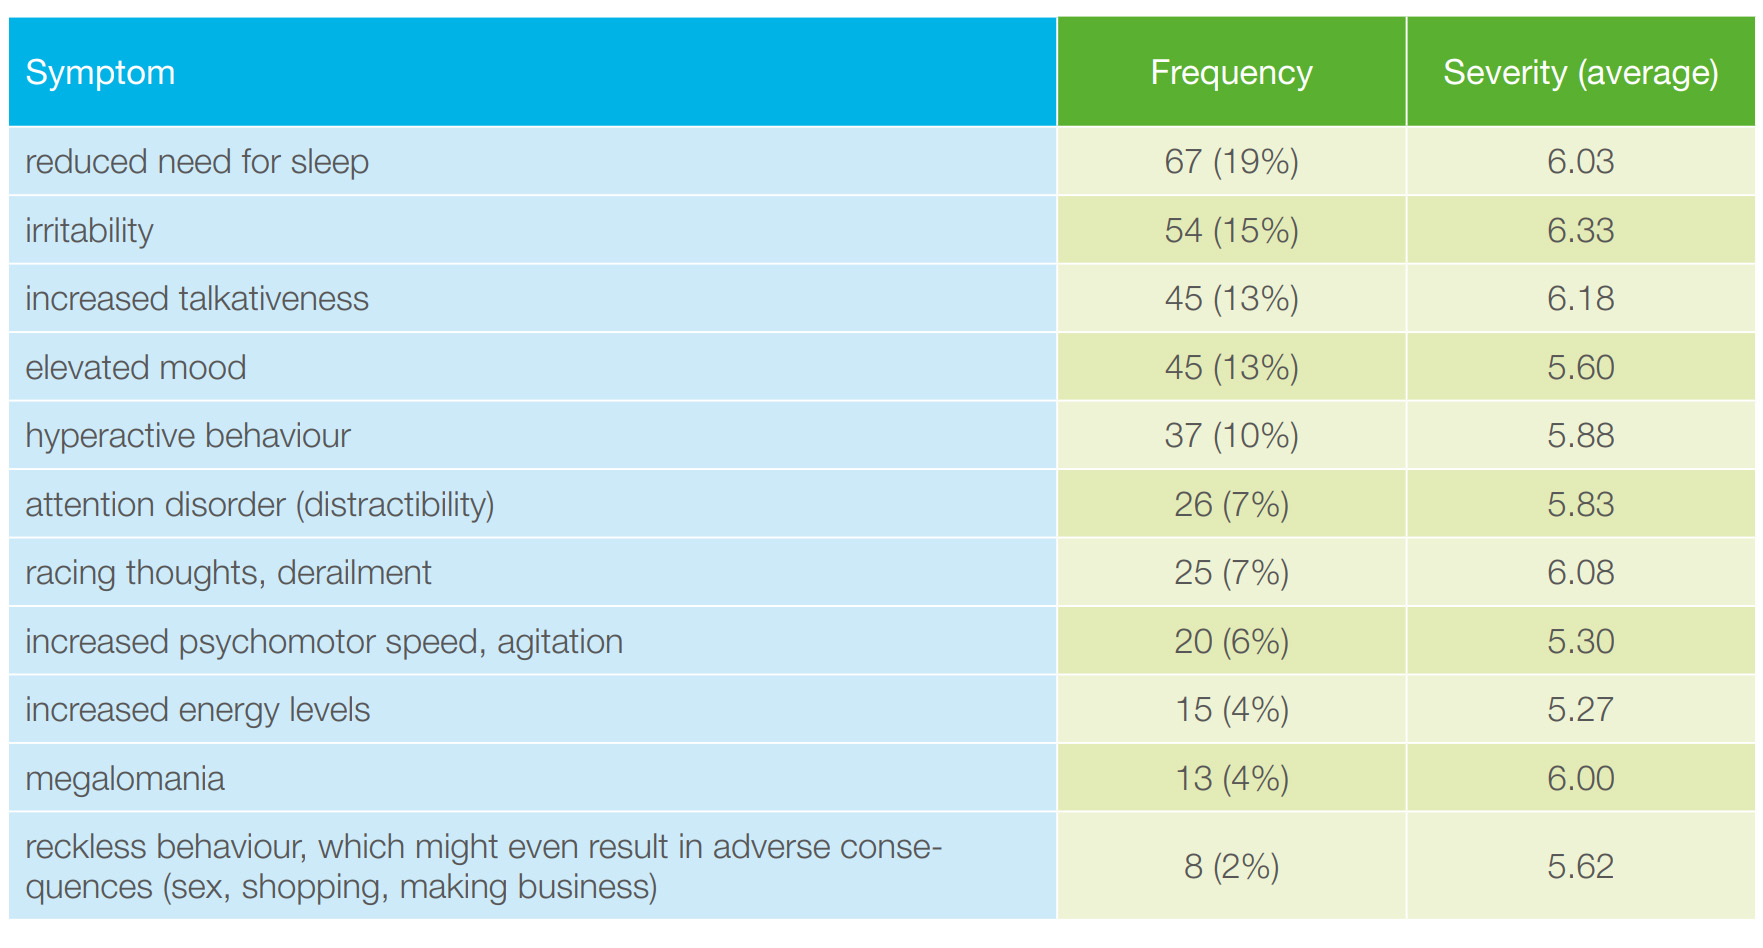
Table 3. Leading symptoms at the start of the study based on physician’s assessment among patients with bipolar I disorder
One and three months after the study began, physicians provided information on the progression of 354 and 351 leading symptoms, respectively. After one month, more than 84% of the symptoms showed at least minimal improvement (Figure 8), and after three months, 93% of the symptoms showed at least minimal improvement compared to the baseline. Only in one case was worsening of any leading symptom reported (Figure 9).
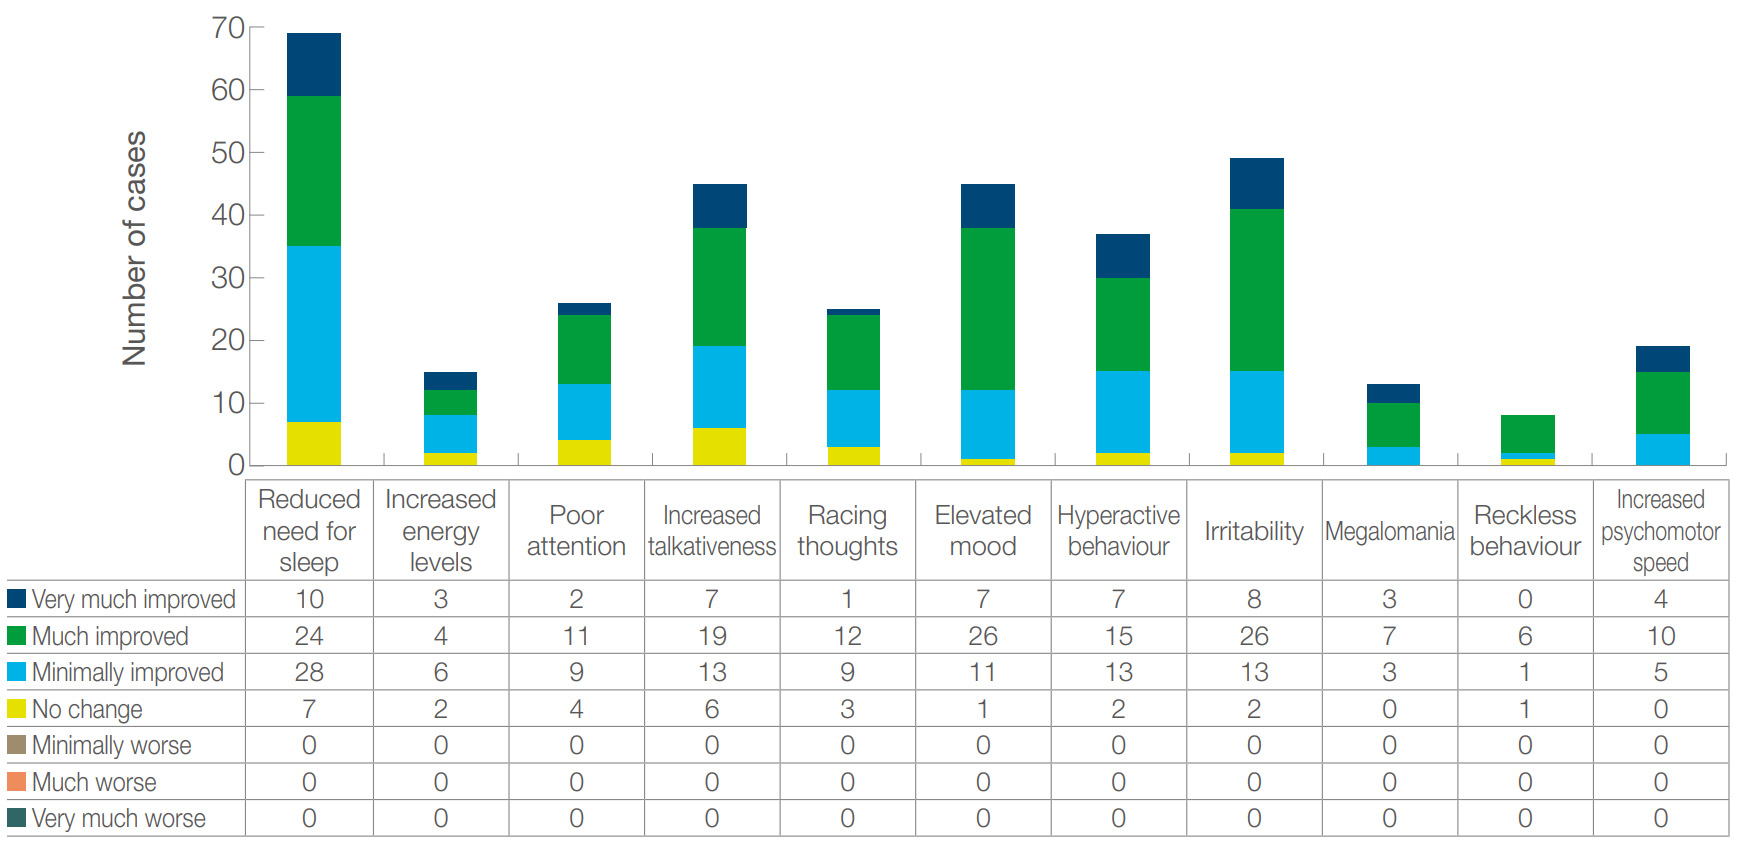
Figure 8 Changes in leading symptoms (n = 355) from the start of the study to the end of the first month among patients with bipolar I disorder
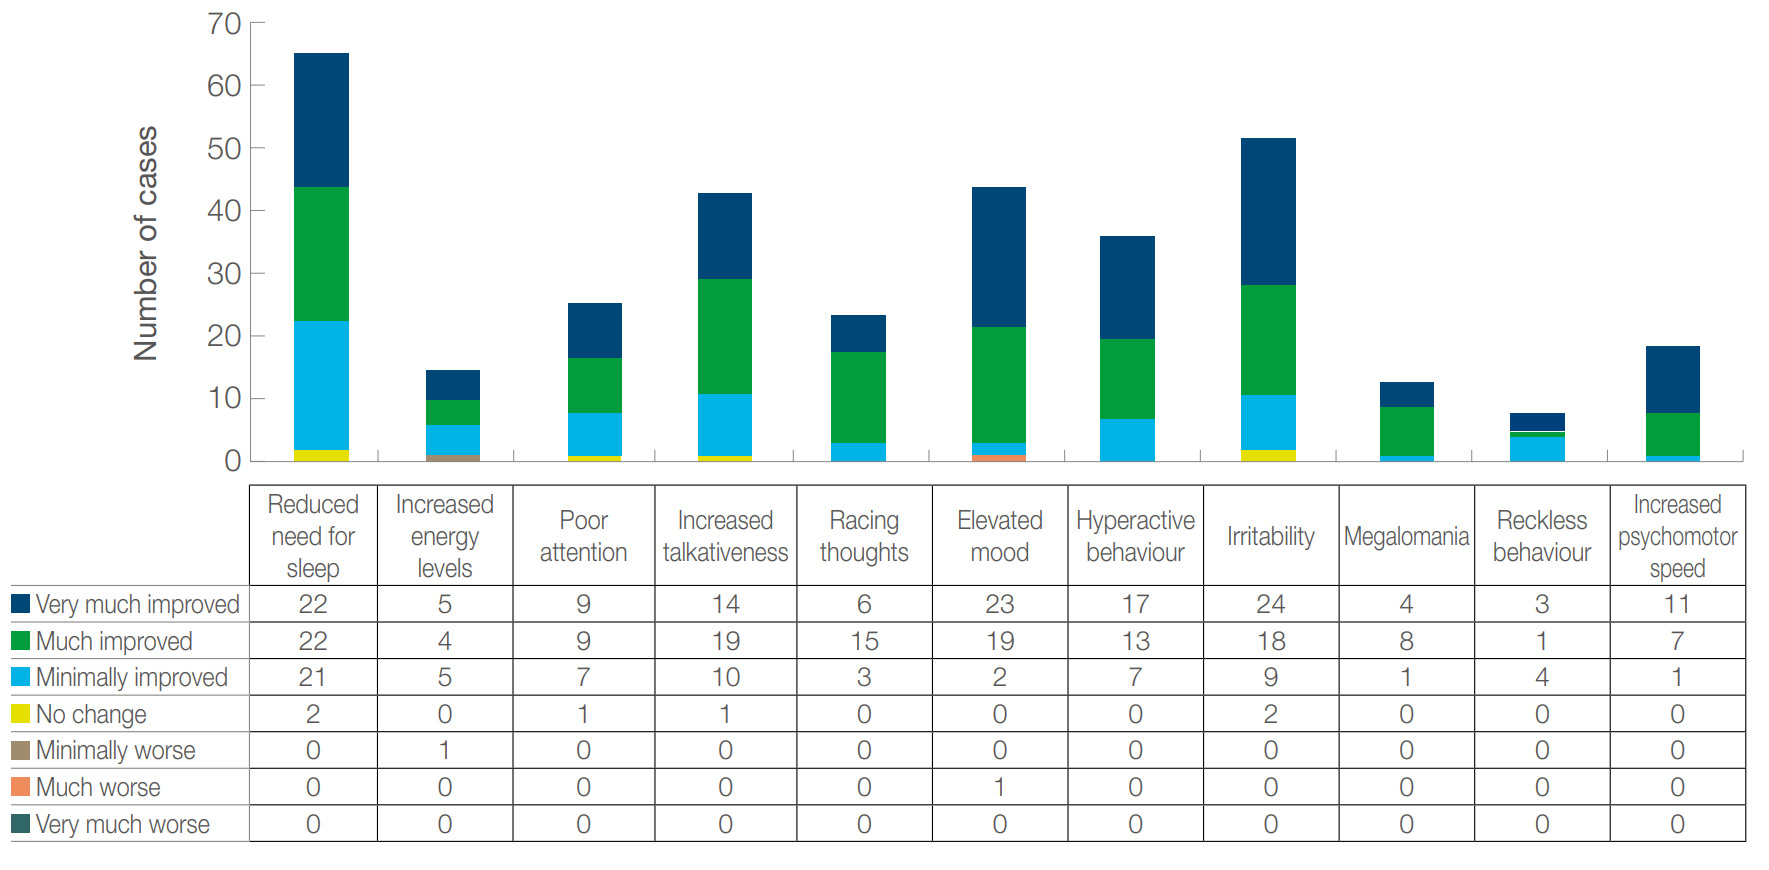
Figure 9 Changes in leading symptoms (n = 355) from the start of the study to the end of the third month among patients with bipolar I disorder
Changes in cognitive function
Changes in cognitive function among patients with schizophrenia
Cognitive functions, specifically conceptual disorganization, difficulty in abstract thinking, and poor attention, were assessed based on the cognition/disorganization components of the PANSS scale during the first, second, and third data collection points. The investigators rated these parameters on a 7-point scale (absent, minimal, mild, moderate, moderate-to-severe, severe, and extreme). A trend of improvement was observed from visit to visit for each parameter assessed.
At baseline, 88% of patients exhibited conceptual disorganization, while after three months, this figure dropped to 63%. The symptom was rated as ‘minimal’ or ‘mild’ in 30% of patients at baseline and in 49% of patients after three months. The proportion of patients classified as ‘moderate’ decreased from 38% to 13%, while the proportion of those with ‘moderate-to-severe’ or ‘severe’ symptoms decreased from 14% to 0%. No patients were classified in the ‘extreme’ category.
Difficulty in abstract thinking affected 98% of patients at baseline, with this figure decreasing to 69% after three months. At baseline, 27% of patients had ‘minimal’ or ‘mild’ symptoms, which increased to 52% after three months. By the end of the third month, the proportion of patients with ‘moderate’ symptoms decreased from 39% to 16%, and those categorized as having ‘moderate-tosevere’ or ‘severe’ symptoms dropped from 26% to 1%. No patients were classified in the ‘extreme’ category.
Poor attention was observed in 97% of patients at baseline, and in 67% after three months.
At baseline, 24% of patients were rated with ‘minimal’ or ‘mild’ symptoms, which increased to 54% after three months. During the three-month treatment period, the proportion of patients with ‘moderate’ symptoms decreased from 39% to 12%, while those categorized as having ‘moderateto-severe’ or ‘severe’ symptoms dropped from 34% to 1%.
The average score for poor attention decreased from 4.01 (±1.09) at baseline to 3.09 (±1.05) after one month, and to 2.34 (±1.09) after three months. A similar decreasing trend was observed for difficulty in abstract thinking (3.71 ±1.27; 2.97 ±1.22; 2.41 ±1.12) and conceptual disorganization (3.49 ±1.31; 2.81 ±1.20; 2.24 ±1.10) (Figure 10).
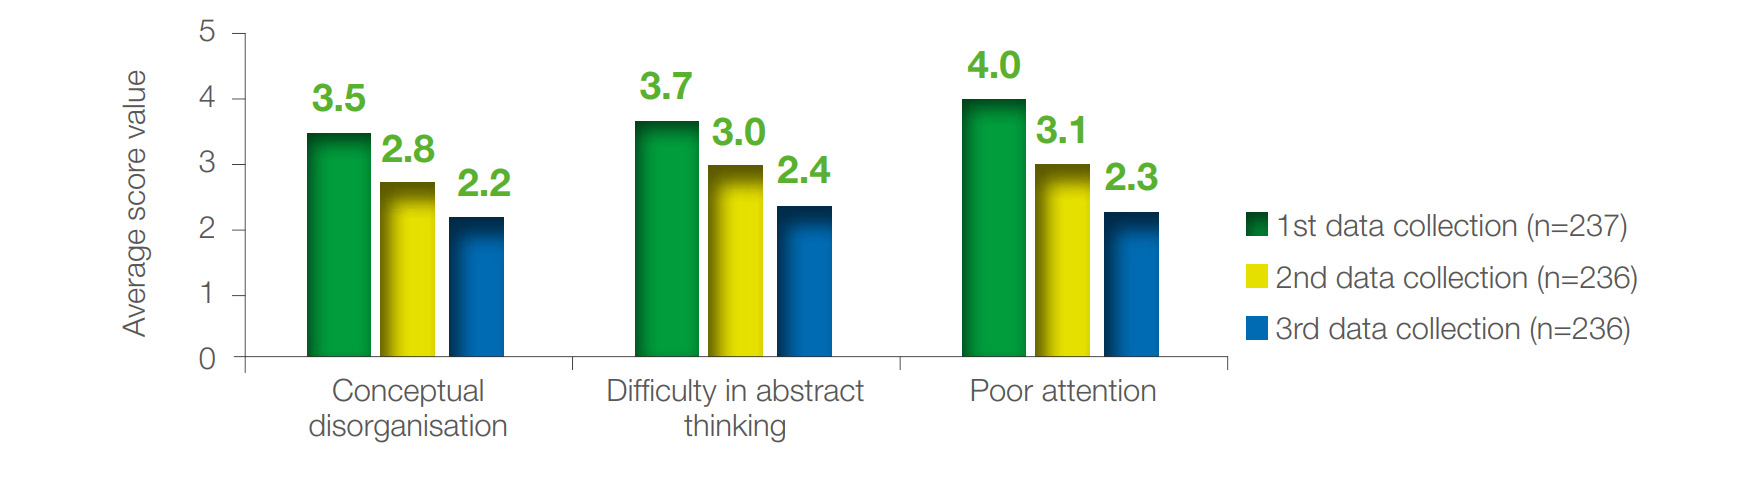
Figure 10 Changes in cognitive function in patients with schizophrenia at baseline, and after the first month and the third month
Changes in cognitive function among patients with bipolar I disorder
Cognitive functions, including conceptual disorganization, difficulty in abstract thinking, and poor attention, showed improvement in all examined parameters over the course of the visits.
At baseline, 58% of patients exhibited conceptual disorganization, while after three months, this figure dropped to 31%. The symptom was rated as ‘minimal’ or ‘mild’ in 30% of patients at baseline and in 29% of patients after three months. The proportion of patients classified as ‘moderate’ decreased from 21% to 3%, while the proportion of those with ‘moderate-to-severe’ or ‘severe’ symptoms decreased from 7% to 0%. No patients were classified in the ‘extreme’ category.
Difficulty in abstract thinking affected 68% of patients at baseline, with this figure decreasing to 49% after three months. At baseline, 37% of patients had ‘minimal’ or ‘mild’ symptoms, which decreased to 33% after three months. The proportion of patients classified as ‘moderate’ decreased from 24% to 6%, while the proportion of those with ‘moderate-to-severe’ or ‘severe’ symptoms decreased from 7% to 0%. No patients were classified in the ‘extreme’ category.
Poor attention was present in 94% of patients at baseline and decreased to 50% by the end of the third month. At baseline, 36% of patients were rated with ‘minimal’ or ‘mild’ symptoms, which increased to 43% after three months. The proportion of patients with ‘moderate’ symptoms decreased from 32% to 7%, while those categorized as having ‘moderate-to-severe’ or ‘severe’ symptoms dropped from 25% to 0%.
The average score for poor attention decreased from 3.60 (±1.23) at baseline to 2.54 (±1.17) after one month, and to 1.93 (±1.03) after three months. A similar decreasing trend was observed for difficulty in abstract thinking (2.59 ±1.33; 2.09 ±1.18; 1.65 ±0.93) and conceptual disorganization (2.41 ±1.39; 1.99 ±1.15; 1.52 ±0.85) (Figure 11).
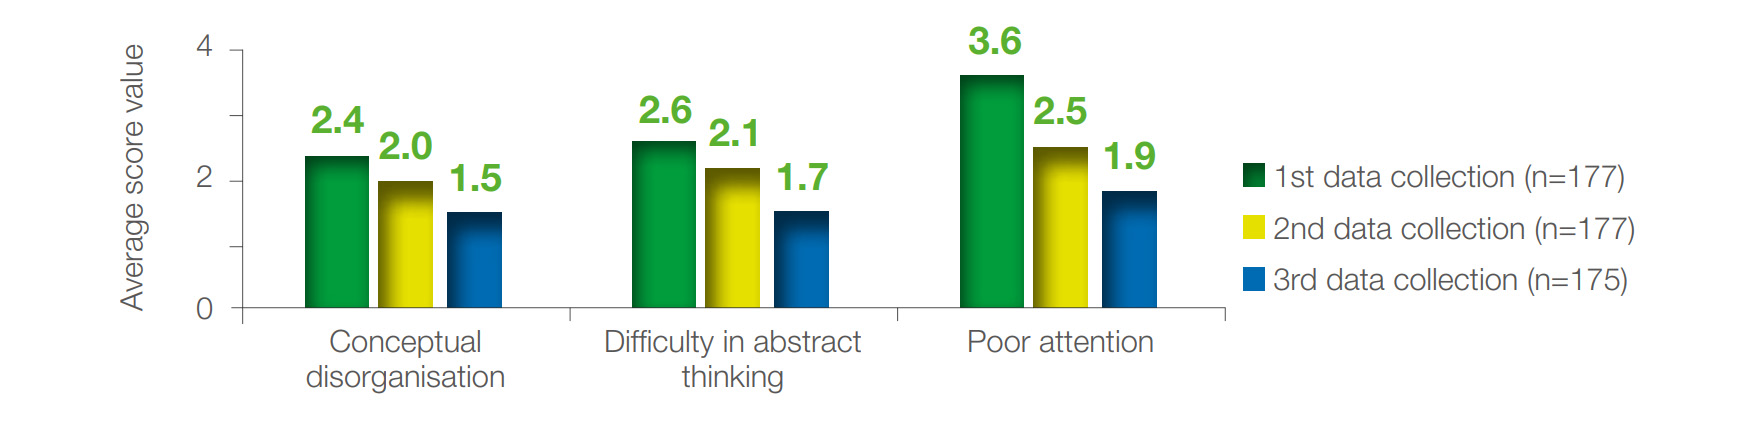
Figure 11 Changes in cognitive function in patients with bipolar I disorder at baseline, and after the first month and the third month
Summary of general cognitive function, social behaviour, and overall well-being assessment
In both diagnostic groups, improvements were observed in general cognitive function, social behaviour, and overall well-being as early as one month after the start of the study, and these improvements became even more pronounced by the end of the third month. (Figures 12–14) For patients with schizophrenia, after one and three months, 67% and 84% of patients showed improvements in general cognitive function; 64% and 85% in social behaviour and relationships; and 80% and 94% in overall well-being, respectively. By the end of the third month, the proportion of patients who ‘much improved’ or ‘very much improved’ reached 51% for general cognitive function, 55% for social behaviour and relationships, and 65% for overall well-being.
For patients with bipolar I disorder, after one and three months, 74% and 84% of patients showed improvements in general cognitive function; 79% and 87% in social behaviour and relationships; and 86% and 92% in overall well-being, respectively. By the end of the third month, the proportion of patients who ‘much improved’ or ‘very much improved’ reached 62% for general cognitive function, 58% for social behaviour and relationships, and 79% for overall well-being.
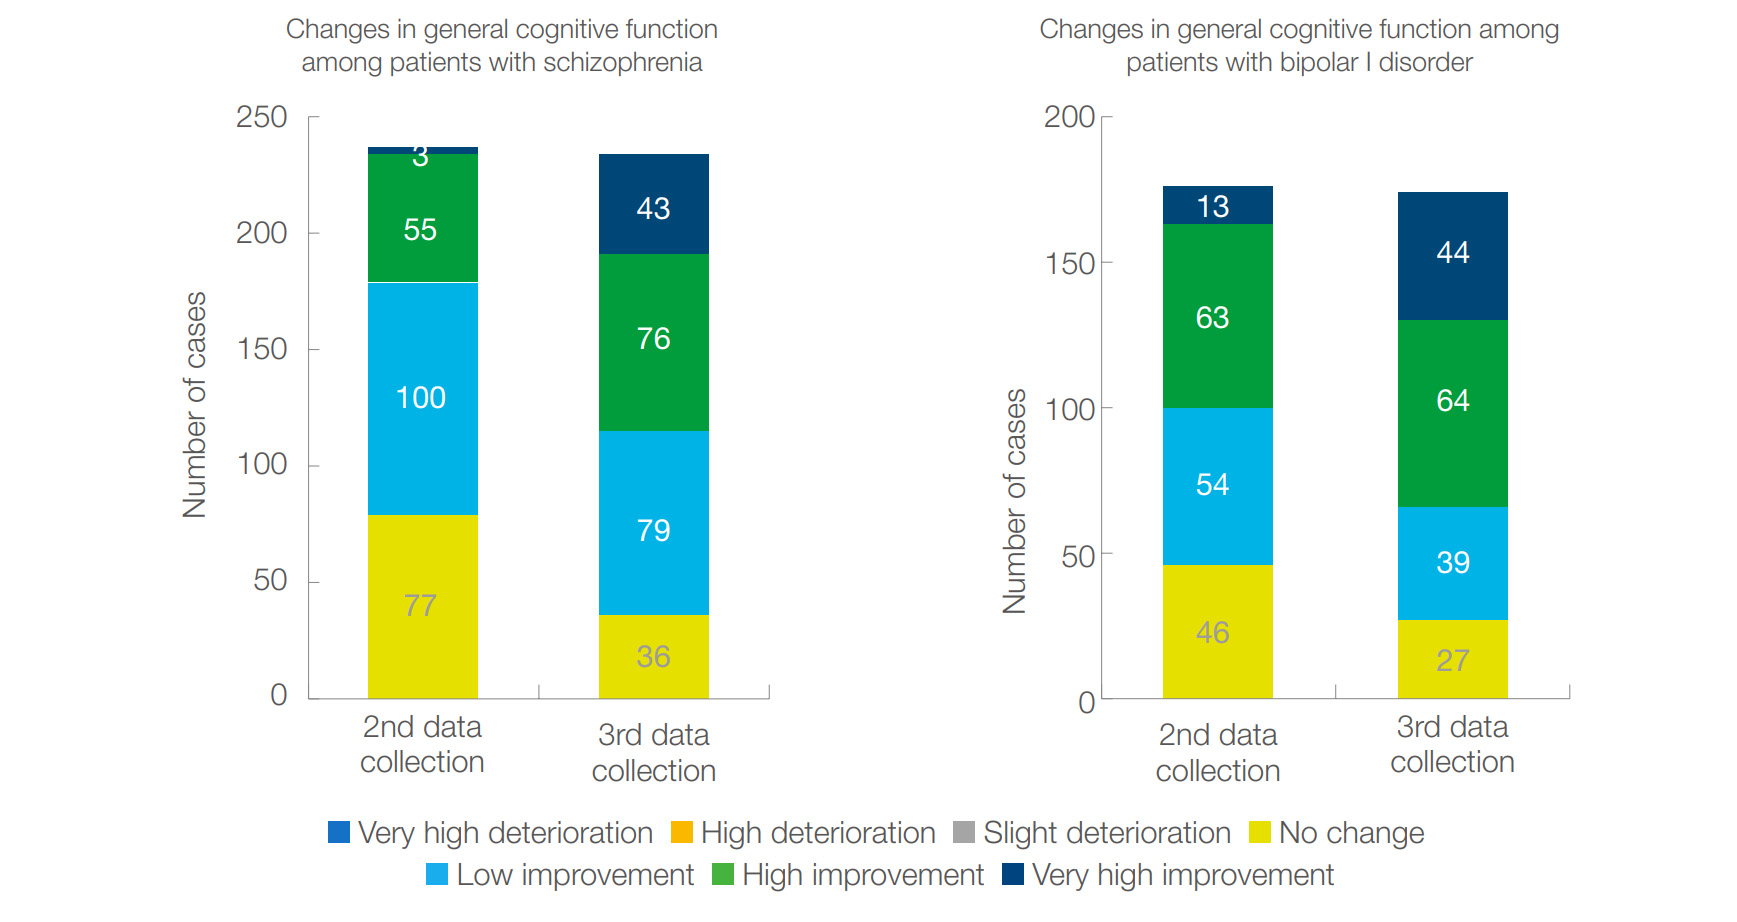
Figure 12 Changes in general cognitive function from the start of the study to the end of the first and the third month among patients with schizophrenia and bipolar I disorder
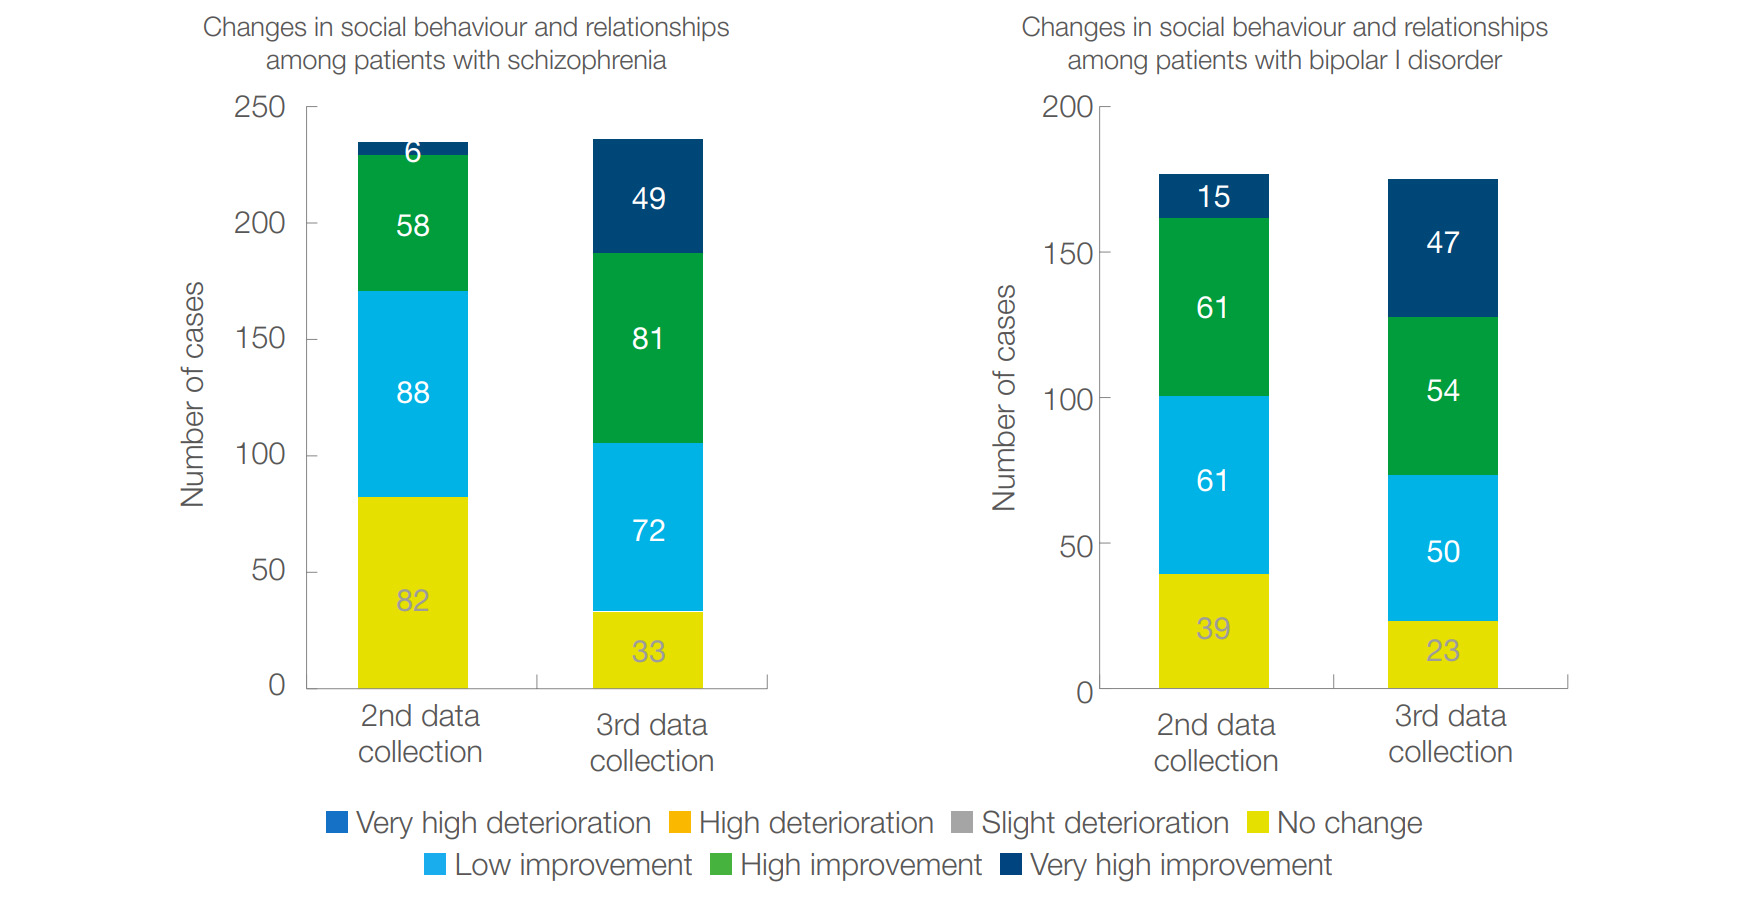
Figure 13 Changes in social behaviour and relationships from the start of the study to the end of the first and the third month among patients with schizophrenia and bipolar I disorder
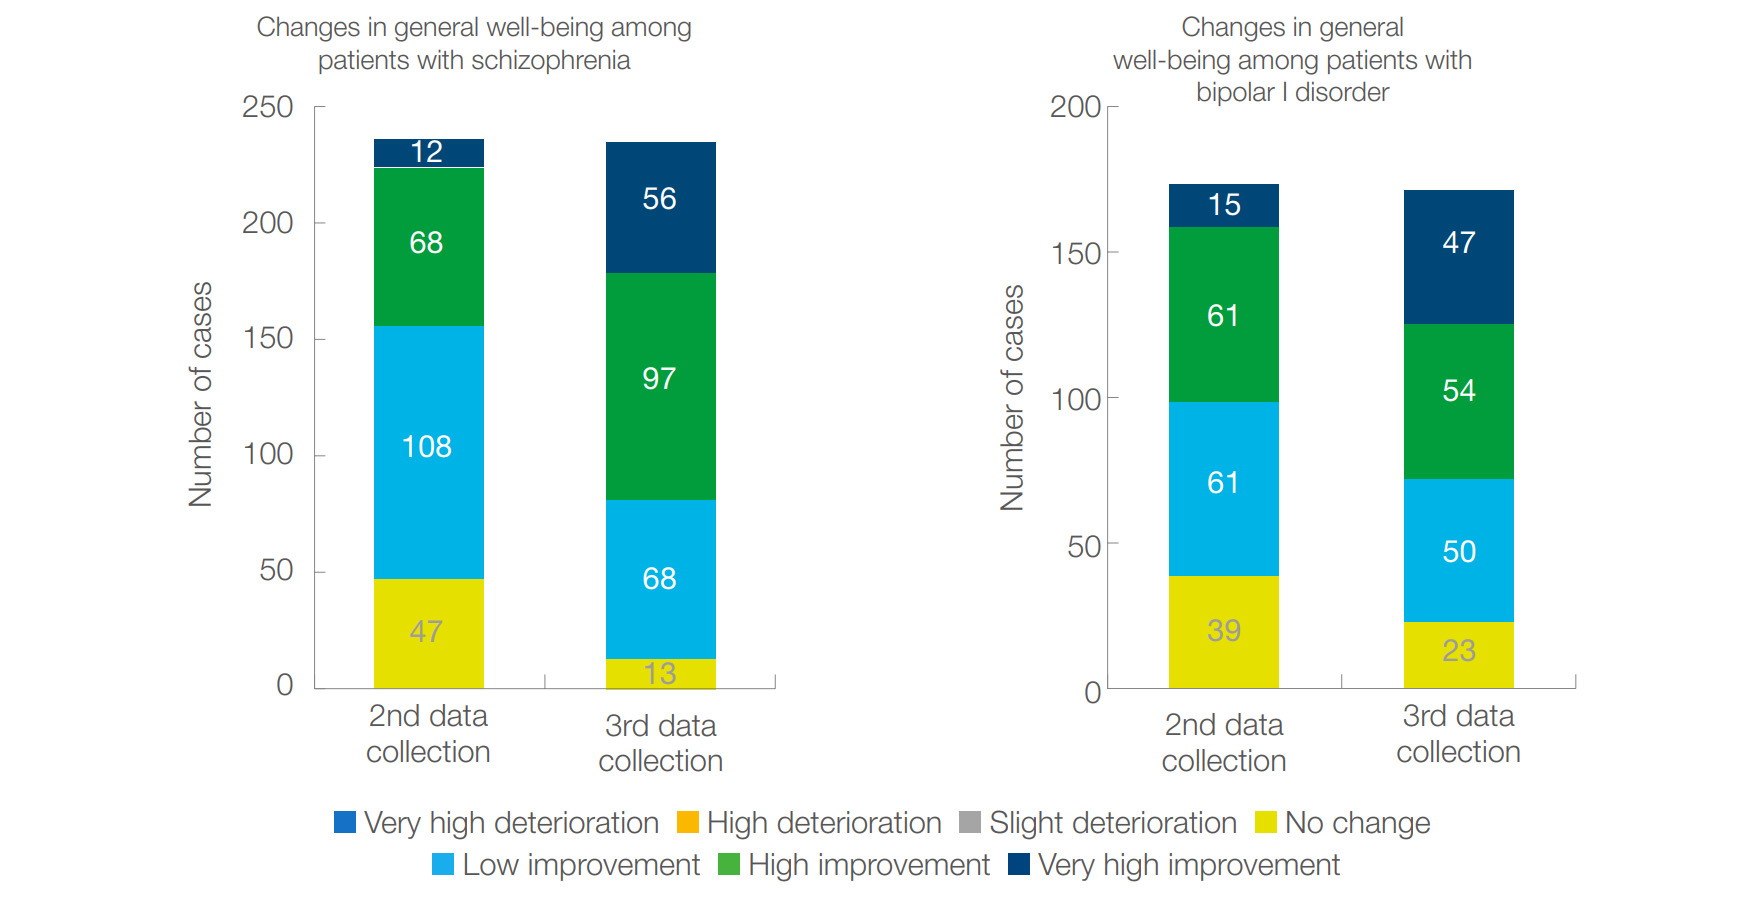
Figure 14 Changes in general well-being from the start of the study to the end of the first and the third month among patients with schizophrenia and bipolar I disorder
Extrapyramidal symptoms and prolactin levels
The prevalence of extrapyramidal symptoms and signs suggesting elevated prolactin levels, which are of major importance in terms of adverse events, remained low throughout the study.
Extrapyramidal symptoms were reported in seven patients (SCH: 6, BD-I: 1) during the first data collection, five patients (SCH: 3, BD-I: 2) during the second data collection, and eight patients (SCH: 6, BD-I: 2) during the third data collection. Symptoms indicating elevated prolactin levels were reported in two patients (BD-I) during the first data collection, one patient (BD-I) during the second and third data collection, and one patient (SCH) during the third data collection.
Out of 14 tests conducted before the second data collection (SCH: 8, BD-I: 6) and nine tests conducted before the third data collection (SCH: 5, BD-I: 4), elevated prolactin levels were confirmed in one case in each period.
Adverse events
The patients tolerated the investigational medication well, with nearly 98% of patients experiencing no adverse events.
During the study, ten adverse events were reported that were considered potentially related to aripiprazole treatment. Nine of these were classified as ‘mild’, while one case (constipation) was considered ‘moderate’.
Among patients with schizophrenia, nausea and vomiting occurred in two cases, while constipation and sedation were each reported in one case.
Among patients with bipolar I disorder, six mild adverse events were reported: akathisia in two cases, and weight gain, dizziness, lack of efficacy, and exacerbation of derealization-depersonalization experiences in one case each. In the latter case, aripiprazole treatment was discontinued. In all other cases, aripiprazole therapy was continued, with dose reduction in two cases and symptomatic treatment applied in one case.
Determination of aripiprazole serum levels
Out of the 34 investigators, only one reported that it would be possible to determine the serum level of aripiprazole in their practice, but they do not usually request such an examination. The other investigation sites responded that it is not possible to request aripiprazole serum level determination at their facilities.
Discussion
It is well known from the literature that low adherence is a major problem in both patients with schizophrenia and bipolar disorder, as proper patient compliance is crucial for treatment success.
A 2022 study by Hsien Li reported that 54.5–80% of patients with schizophrenia did not take their medication regularly, leading to recurring psychiatric symptoms and repeated hospitalisations (Hsien Li et al., 2023).
Among patients with bipolar disorder, approximately 60% did not fully adhere to medicinal regimen within one year after an episode. This was associated with low remission rates, an increased risk of relapse, residual symptoms, and psychosocial impairment (Colom et al., 2005; Erdélyi-Hamza et al., 2021).
In the CATIE (Clinical Antipsychotic Trials of Intervention Effectiveness) study conducted in the USA, 74% of patients with schizophrenia discontinued treatment within 18 months (Lieberman et al., 2005).
A Hungarian study conducted in 2019 analysed the admission of patients with schizophrenia to the psychiatric care system. It was found that approximately 70% of newly diagnosed patients with schizophrenia discontinued medication within the first few months after initiation. However, over the subsequent four years, the drop-out rate was significantly lower. The authors concluded that patients with poor insight into their illness often do not engage with the healthcare system, whereas those who actively seek regular care are more likely to remain within the psychiatric treatment system (Makkos et al., 2019).
Medication adherence is a complex phenomenon influenced by factors related to the patient (age, duration of illness, psychopathological symptoms, comorbidities, alcohol dependence or other illicit medication use, the environment (social status, family and social relationships), the healthcare system, and the medication itself (efficacy, side effects, applicability) (El-Mallakh & Findlay 2015; Acosta et al., 2012).
In our study, during the 12-week observational period, 99% of the 414 patients receiving aripiprazole treatment remained on therapy.
This high persistence rate was likely influenced not only by the high efficacy, favourable side-effect profile, and long-term tolerability of aripiprazole but also by patient selection criteria. The study included patients over 18 years of age, mostly with a long treatment history spanning decades, without limited legal capacity, who voluntarily participated and had no conditions preventing participation. Additionally, the doctor-patient relationship likely played a role in adherence.
The predominance of patients with a long treatment history spanning decades in the study may also be related to the Hungarian reimbursement protocol for aripiprazole. In schizophrenia, it is only reimbursed as a second-line treatment, while in bipolar disorder, it is eligible for special reimbursement in mania as the fourth-line treatment (NEAK – National Health Insurance Fund of Hungary, priority indication 01/07/2024).
According to physicians’ assessment, after one month of treatment, patient adherence in both patient groups seemed problem-free for three quarters of the patients, and remained largely unchanged (in about 80%) by the end of the third month, with a slight increase in the proportion of BD-I patients who appeared to be problem-free.
Due to the different methodologies, the assessment of adherence by physicians and patients cannot be objectively compared. However, patients’ self-reports appeared slightly worse than physicians’ assessments. According to self-reports, 55% of patients classified themselves in the high adherence group after one month, and 57% after three months, indicating a largely stable adherence level. In the bipolar I disorder group, the proportion of patients in the high adherence group increased from 54% to 61% by the end of the third month. Additionally, the proportion of patients in the low adherence group also increased by 3%, reaching 6% after one month and 9% after three months.
At baseline, higher doses of aripiprazole were prescribed for patients with schizophrenia. The lowest 10 mg dose was used in 32% of patients with schizophrenia and 49% of patients with bipolar I disorder. The highest 30 mg dose was administered to 21% of patients with schizophrenia and 14% of patients with bipolar I disorder. During the three-month observation period, the aripiprazole dose was adjusted in 22% of patients across both diagnoses, mostly increasing to higher doses.
However, concomitant use of other antipsychotic and mood-stabilising treatments adds complexity to these findings.
At baseline, 29% of patients with schizophrenia and 18% of patients with bipolar I disorder received combination therapy with another antipsychotic. Additionally, 4% of patients with schizophrenia and 51% of patients with bipolar I disorder were on concomitant mood-stabilising treatment. Current clinical guidelines for the treatment of bipolar disorder recommend lithium or valproate in combination with aripiprazole as a first-line choice for mania management (Hungarian Ministry of Human Resources, 2016). In this regard, adherence to guidelines in our study was relatively low.
Literature suggests that both schizophrenia and bipolar disorder have a high prevalence of comorbid anxiety and depressive disorders, as well as substance and/or alcohol use issues.
In our study, comorbid psychiatric disorders (most commonly anxiety disorders) were present in 29% of patients, which is lower compared to literature data (Buckley et al., 2009; Hungarian Ministry of Human Resources, 2016).
The lower rate of substance/alcohol dependence in our sample can be attributed to patient screening and exclusion.
The severity of the disease showed a gradual improvement in both patient groups between visits.
The improving trend was clearly observed in both groups, based on the CGI-S and CGI-I scale data recorded during the second and third data collection points.
The CGI-S scores decreased from 4.45 to 3.86 and then to 3.33 in schizophrenia, and from 4.38 to 3.5 and then to 2.92 in bipolar I disorder.
According to CGI-I scores, 96% of patients ‘much improved’ or ‘very much improved’ after three months. 69% of patients with schizophrenia and 81% of patients with bipolar I disorder ‘much improved’ or ‘very much improved’.
In schizophrenia, the most common leading symptoms were negative symptoms (30%) and delusions (28%).
In bipolar I disorder, the symptom profile showed greater variability due to a broader range of available symptom categories. Among the 12 specified symptoms, the most frequently reported were reduced need for sleep (19%), irritability (15%), elevated mood (13%), and increased talkativeness (13%).
The severity of symptoms, based on scores, was categorized as ‘moderate’ for all leading symptoms, with slightly higher average values in bipolar I disorder.
By the end of the third month, more than 90% of symptoms had improved in both diagnoses (SCH: 94%, BD-I: 93%).
Cognitive impairment is a fundamental characteristic of both schizophrenia and bipolar disorder. The neuropsychological profiles of the two patient groups overlap, with differences being more quantitative. Cognitive deficits can be identified early in both disorders, during the first manic or psychotic episode. However, in schizophrenia, impairments are generally more severe and often present before symptom onset, which is true for some subgroups in bipolar disorder. It is still unclear how the neuropsychological basis of cognitive impairments differs between the two conditions (Bortolato et al., 2015, McCutcheon et al.,2023).
Although literature suggests that all antipsychotics have similarly small effects on cognitive function (McCutcheon et al., 2023), in this study, cognitive function showed a gradual improvement alongside the general symptomatic relief observed with aripiprazole treatment.
The gradual symptom improvement in both diagnostic groups extended to all cognitive functions, including conceptual disorganization, difficulty in abstract thinking, and poor attention.
Based on the cognition/disorganization components of the PANSS scale (conceptual disorganization, difficulty in abstract thinking, poor attention), the baseline scores for all functions in schizophrenia exceeded those observed in bipolar I disorder, but the decrease was evident in both disorders.
Gradual improvement was also observed in general cognitive functioning, social behaviour, and overall well-being, similar to the previous findings.
Patients tolerated aripiprazole treatment well throughout the study, with nearly 98% experiencing no adverse events. The only serious adverse event was hospitalization due to relapse caused by medication discontinuation. Among the 10 mostly mild suspected adverse events were vomiting, nausea, akathisia, weight gain, vertigo, constipation, and sedation. These cases fit within the known adverse events profile of the medication. Gastrointestinal symptoms are often transient. Aripiprazole has a favorable metabolic profile, causing minimal weight gain and typically not inducing hyperprolactinemia (Citrome, 2006). Consistent with this, only 2 out of 23 prolactin level tests during the study showed elevated prolactin levels.
The enzymes involved in aripiprazole metabolism exhibit significant individual variability. Continuous monitoring of aripiprazole blood levels can help avoid lack of efficacy and adverse events (Kirschbaum et al., 2008; Hiemke et al., 2018), supporting personalized treatment. According to study data, determining aripiprazole blood levels is not part of daily practice in our country, and no such measurements were performed during treatment.
The study conducted in real-world settings confirmed that aripiprazole, whether as monotherapy or combination therapy, can be an effective and well-tolerated solution for the treatment of schizophrenia and for the treatment and prevention of mania in bipolar I disorder.
DECLARATION: This study was sponsored by KRKA. The authors participating in the study received financial compensation for their professional contributions during the research. The financial support facilitated the conduct of the research, data analysis, and the publication process. The sponsorship did not influence the results, conclusions, or professional independence of the study.
References
- Acosta, F. J., Hernández, J. L., Pereira, J., Herrera, J., Rodríguez, C. J. (2012) Medication adherence in schizophrenia, World J Psychiatr 2: 74-82.
- Anderson, A. E., Mansolf, M., Reise, S. P., Savitz, A., Salvadore, G., Li, Q., Bilder, R. M. (2017) Measuring pathology using the PANSS across diagnoses: Inconsistency of the positive symptom domain across schizophrenia, schizoaffective, and bipolar disorder Psychiatry Res. December; 258: 207–216.
- Bortolato, B., Miskowiak, K. W., Köhler, C. A., Carvalho, A. F. (2015) Cognitive dysfunction in bipolar disorder and schizophrenia: a systematic review of meta-analyses, Neuropsychiatric Disease and Treatment 11:3111–3125.
- Buckley, P. F., Miller, B. J., Lehrer, D. S., Castle, D. J. (2009) Psychiatric Comorbidities and Schizophrenia, Schizophrenia Bulletin 35: 383–402.
- Busner, J., Targum, S. D. (2007) The Clinical Global Impressions Scale: Applying a Research Tool in Clinical Practice, Psychiatry July 29-37.
- Citrome, L. (2006) A review of aripiprazole in the treatment of patients with schizophrenia or bipolar I disorder, Neuropsychiatric Disease and Treatment:2:427–443.
- Colom, F., Vieta, E., Tacchi, M. J., Sanchez-Moreno, J., Scott, J. (2005) Identifying and improving non-adherence in bipolar disorders. Bipolar Disord7 (Suppl 5): 24–31.
- El-Mallah, P., Findlay, J. (2015) Strategies to improve medication adherence in patients with schizophrenia: the role of support services Neuropsychiatric Disease and Treatment 11:1077–1090.
- Erdélyi-Hamza, B., Elek, L. P., Gonda, X. (2021) Le lehet-e szállni a hullámvasútról? A bipoláris affektív zavarok pszichoterápiás kezelésének lehetőségei, Neuropsychopharmacol Hung. 23: 296– 307.
- Hiemke, C., Bergemann, N., Clement, H. W., Conca, A., Deckert, J., Domschke, K., Eckermann, G., Egberts, K.,Gerlach, M., Greiner, Gründer, G., Haen, E., Havemann-Reinecke, U., Hefner, G., Helmer, R., Janssen, G., Jaquenoud, E., Laux, G., Messer, T., Mössner, R., Müller, M. J., Paulzen, M., Pfuhlmann, B., Riederer, P., Saria, A., Schoppek, B., Schoretsanitis, G., Schwarz, M., Silva Gracia, M., Stegmann, B., Steimer, W., Stingl, J. C., Uhr, M., Ulrich, S., Unterecker, S., Waschgler, R., Zernig, G., Zurek, G., Baumann, P. (2018) Consensus Guidelines for Therapeutic Drug Monitoring in Neuropsychopharmacology: Update 2017 Pharmacopsychiatry 51:9–62.
- Hsien, I. L., Hsieh W. L., Liu W. I. (2023) A Systematic Review and Meta-Analysis of the Effectiveness of Adherence Therapy and Its Treatment Duration in Patients with Schizophrenia Spectrum Disorders, Patient Preference and Adherence 17:769–780.
- Kikuchi, T., Maeda, K., Suzuki, M., Hirose, T., Futamura, T., McQuade, R. D. (2021), Discovery research and development history of the dopamine D2 receptor partial agonists, aripiprazole and brexpiprazole Neuropsychopharmacol Rep.; 41:134–143.
- Kirschbaum, K. M., Müller, M. J., Malevani, J., Mobascher, A., Burchardt, C., Piel, M., Hiemke, C. (2008) Serum levels of aripiprazole and dehydroaripiprazole, clinical response and side effects The World Journal of Biological Psychiatry, 2008; 9: 212-218.
- Lieberman, J. A., Stroup, T. S., McEvoy, J. P., Swartz, M. S., Rosenheck, R. A., Perkins, D. O., Keefe, R. S. E., +5, for the Clinical Antipsychotic Trials of Intervention Effectiveness (CATIE) Investigators (2005) Effectiveness of Antipsychotic Drugs in Patients with Chronic Schizophrenia, N Engl J Med 353:1209-1223.
- Makkos, Z., Kováts, T., Gaál, P. (2019) Antipszichotikum gyógyszerkiváltási adatok és szkizofrén betegek pszichiátria ellátórendszerben való megjelenésének elemzése, Neuropsychopharmacol Hung 21): 164–169.
- McCutcheon, R. A., Keefe, R. S. E., McGuire, P. K. (2023) Cognitive impairment in schizophrenia: aetiology, pathophysiology, and treatment, Molecular Psychiatry 28:1902–1918.
- McIntyre, R. S., Daniel, D. G., Vieta, E., Laszlovszky, I., Goetghebeur, P. J., Earley, W. R., Patel, M. D. (2023) The efficacy of cariprazine on cognition: a post hoc analysis from phase II/III clinical trials in bipolar mania, bipolar depression, and schizophrenia CNS Spectrums 28(3), 319–330.
- Morinsky, D. E., Green L. W., Levine D. M. (1986) Concurrent and Predictive Validity of a Self-reported Measure of Medication Adherence, MEDICAL CARE Vol. 24, No. 1.
- Rodriguez-Jimenez, R., Bagney, A., Mezquita, L., Martinez-Gras, I., Sanchez-Morla, E. M., Mesa, N., Manuel-Ibañez, I., DiezMartin, J., Jimenez-Arriero, M. A., Lobo, A., Santos, J. L., Palomo, T., and PARG (2012) Cognition and the five-factor model of the Positive and Negative Syndrome Scale in schizophrenia, Schizophrenia Research 143:77-83.
- Sümegi A. (2014) Szkizofrén beteg: az adherenciaproblémák jelentősége, Pharma Online archivum https://pharmaonline.hu/ cikk/szkizofren_beteg az_adherenciaproblemak_jelentosege (Last accessed: 15.07.2024)
- Wallwork, R. S., Fortgang, R., Hashimoto, R., Weinberger, D. R., Dickinson, D., (2012). Searching for a consensus!ve-factor model of the Positive and Negative Syndrome Scale for schizophrenia. Schizophr. Res. 137, 246–250
- Arisppa® Summary of Product Characteristics 10 April 2023.
- Emberi Erőforrások Minisztériuma – Egészségügyért Felelős Államtitkárság Egészségügyi Szakmai Kollégium: Egészségügyi szakmai irányelv – A bipoláris affektív betegségek diagnosztikájáról és terápiájáról 2016. https://kollegium.aeek.hu/Iranyelvek/Index (Last accessed: 15.07.2024)
- NEAK-közlemény a finanszírozási eljárásrendekről; A szkizofrénia antipszichotikus gyógyszeres kezelésének finanszírozási eljárásrendje Page 273, Section 1. https://www.neak.gov.hu/pfile/file?path=/felso_menu/szakmai_oldalak/finanszirozasi_protokollok/hatalyos/hatalyos_neak-kozlemeny-afinanszirozasi-eljarasrendekrolegyesitett_20240104&inline=true (Last accessed: 15.07.2024)
- NEAKA kiemelt indikációhoz kötött támogatási kategóriába tartozó betegségcsoportok, indikációs területek és felírásra jogosultak köre 2024.07.01 https://www.neak.gov.hu/pfile/file?path=/letoltheto/ATFO_dok/ gyogyszer/ind/EU_kiemelt_tamogatasi_lista_2024_07_01.pdf1&inline=true (Last accessed: 15.07.2024)
Authors
Ágota Mészáros
Krka Magyarország Kft., Budapest
Judit Pákó
Krka Magyarország Kft., Budapest
György Szekeres
PhD, Department of Psychiatry and Psychotherapy, Semmelweis University, Budapest
Krka’s medicines are marketed in different countries under different brand names.
Some products may not be available in all countries due to still valid patent protection.
For complete information on the products please refer to the Summary of Product Characteristics. You can obtain it from Krka’s medical representatives.
We have compiled a collection of scientific papers in which we present the rich experience obtained from the clinical studies with Krka’s medicines.
Published: September 2024